Today’s chatbots aren’t likely to help lone actors invent a deadly pathogen, experts say. But newer models, trained in biology, may need stronger safeguards.
In women's reproductive years, their brains are exposed to high levels of sex hormones, and their neurons may come to depend on those hormones to function optimally. But leading up to and after menopause, the ovaries produce far less estrogen and progesterone, raising concerns that this drop in hormones may contribute to women's dementia risk.
"We think that the loss of those hormones at menopause renders those neurons more vulnerable to age-related cellular decline and pathologies like Alzheimer's," said Karyn Frick, a neuroscientist and professor of psychological and brain sciences at the University of Wisconsin-Milwaukee.
So, if falling hormone levels are a risk factor for dementia, could replacing those hormones help stave off the disease?
While the idea sounds logical on its face, studies that have looked at hormone replacement therapy (HRT) for dementia prevention have had mixed results. There are early hints that restoring estrogen during early menopause may protect brain health, but ultimately, more gold-standard clinical trials are needed to know for sure, experts told Live Science.
Support for estrogen protecting the brain
The idea that estrogen could help ward off dementia is plausible. Women are more likely to develop Alzheimer's disease than men are, and scientists think the loss of estrogen during menopause may be partly to blame, said Jennifer Bruno, an instructor of psychiatry and behavioral sciences at Stanford University.
Lab and animal studies buttress the idea that estrogen could protect brain health.
In the brain, estrogens act as neuromodulators, or chemical messengers that alter how neurons behave. Estrogen also helps neurons keep their shape. Estrogen loss in female mice triggers a drop in the number of dendritic spines — the small, bud-like bumps on neurons that receive chemical messages.
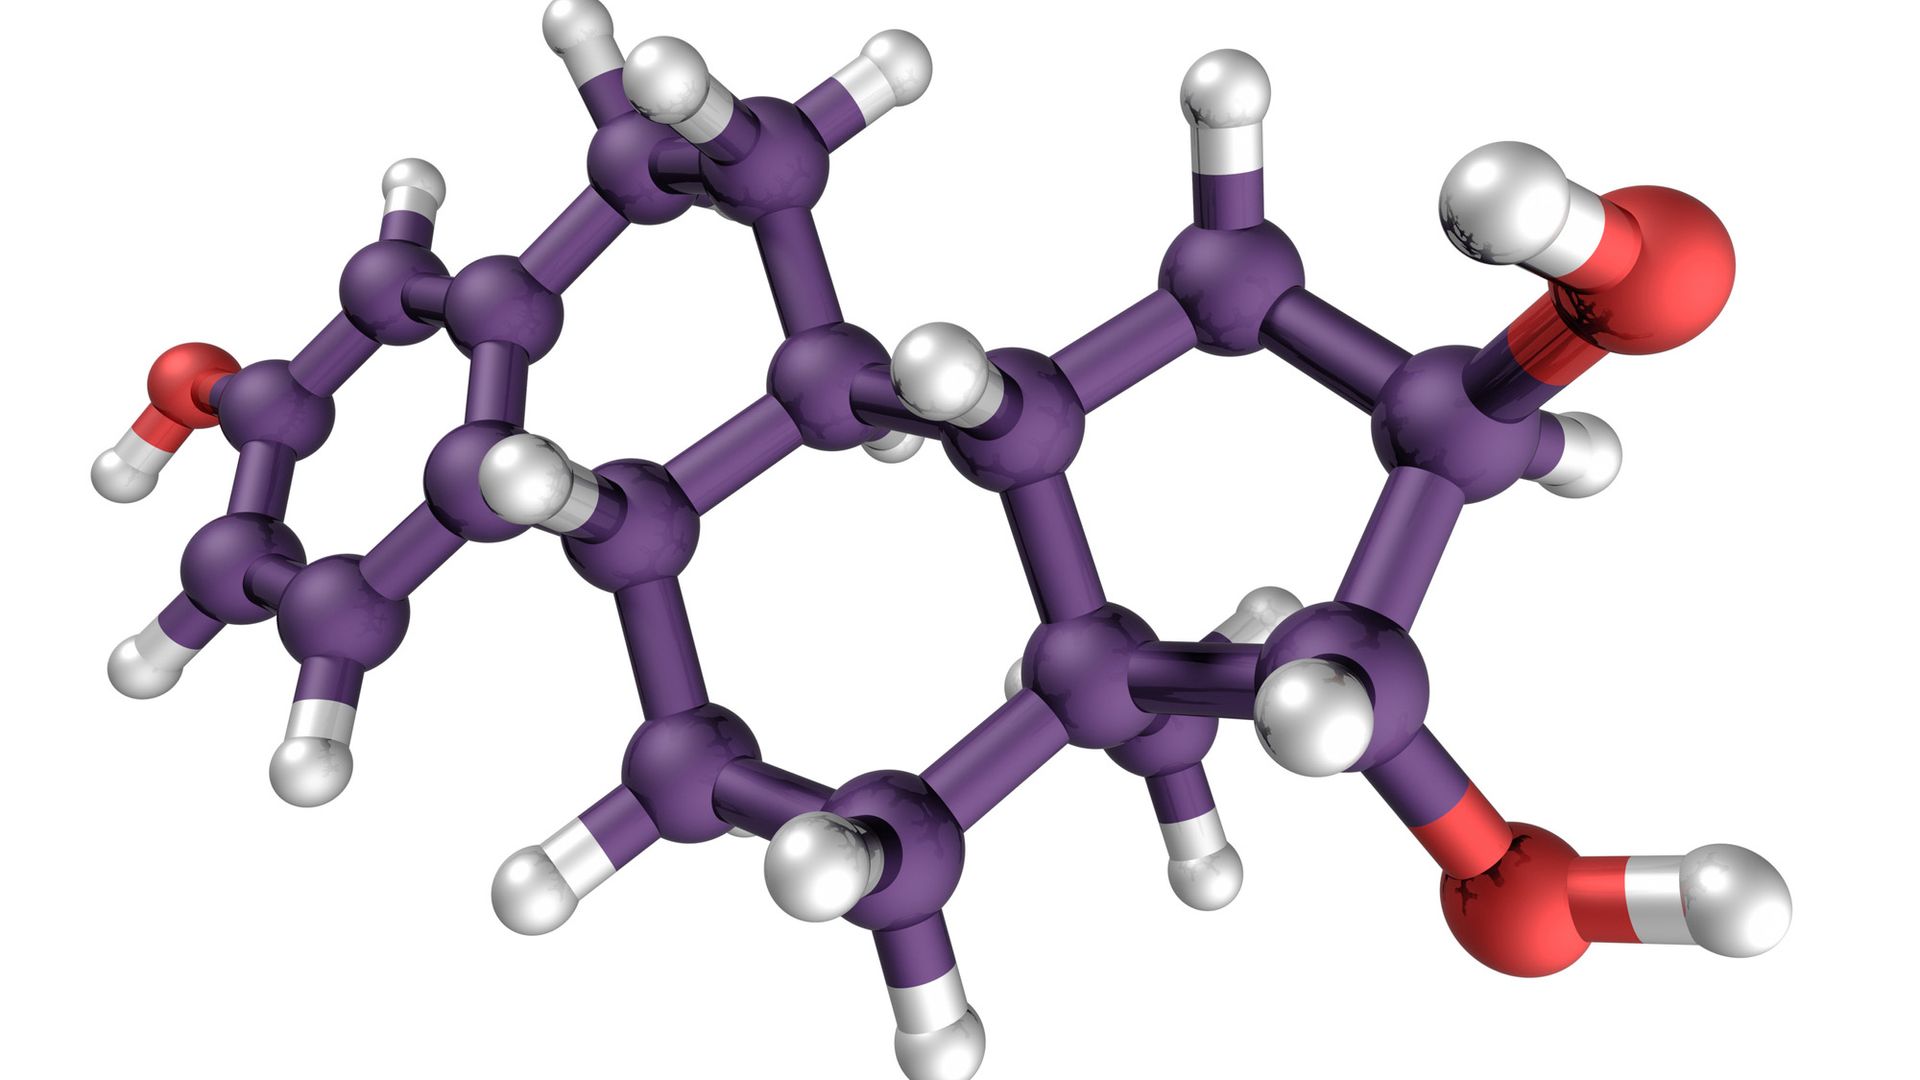
An estrogen molecule. The body's levels of estrogen fluctuate in perimenopause, and they then dramatically decline and level off during and after menopause. (Image credit: theasis via Getty Images)
Researchers think that estrogen may help prevent the formation of the abnormal proteins — including one called amyloid beta — that accumulate, disrupt communication between neurons and ultimately kill cells in Alzheimer's disease. Amyloid beta is produced when a larger protein is cut the "wrong" way by an enzyme, Frick explained. Estrogen promotes the "normal" cutting of this protein, thus reducing amyloid beta, studies in lab mice show.
And estrogen may limit the buildup of a second Alzheimer's-related protein, called tau, by preventing the chemical processes that cause the tau proteins to clump together. This helps prevent the formation of tau tangles, a hallmark of Alzheimer's disease.
The hormone may also support brain health indirectly by improving sleep quality.
"It's well documented that menopausal women have difficulty sleeping, whether it's due to hot flashes or insomnia," Frick said. Estrogen can ease those nighttime hot flashes, thus helping menopausal women get more, less-fragmented sleep. Deep rest may help the brain clean out toxic proteins, while research shows sleep deficiency is linked to Alzheimer's disease.
Mixed results with estrogen-only HRT
HRT for menopause comes in two main forms: treatments that include only estrogen, and combined therapies with both estrogen and progesterone. The treatment has a complicated history.
That said, the Women's Health Initiative study found that estrogen-only HRT came with an increased risk of endometrial cancers, and later analyses have backed up this idea. That's why today, clinical guidelines recommend that women who have not gotten a hysterectomy take combined HRT, while estrogen-only options are reserved for those who have had their uterus removed. (The added progesterone counteracts estrogen's thickening effect on the uterine lining.)
For the subset of women who take estrogen-only HRT, observational data published in August showed that this form of the treatment was linked to a reduced risk of dementia. The study, published in the journal Neurology, found that women who took estrogen-only HRT were less likely to show Alzheimer's-related changes in the brain than women who didn't take any HRT.
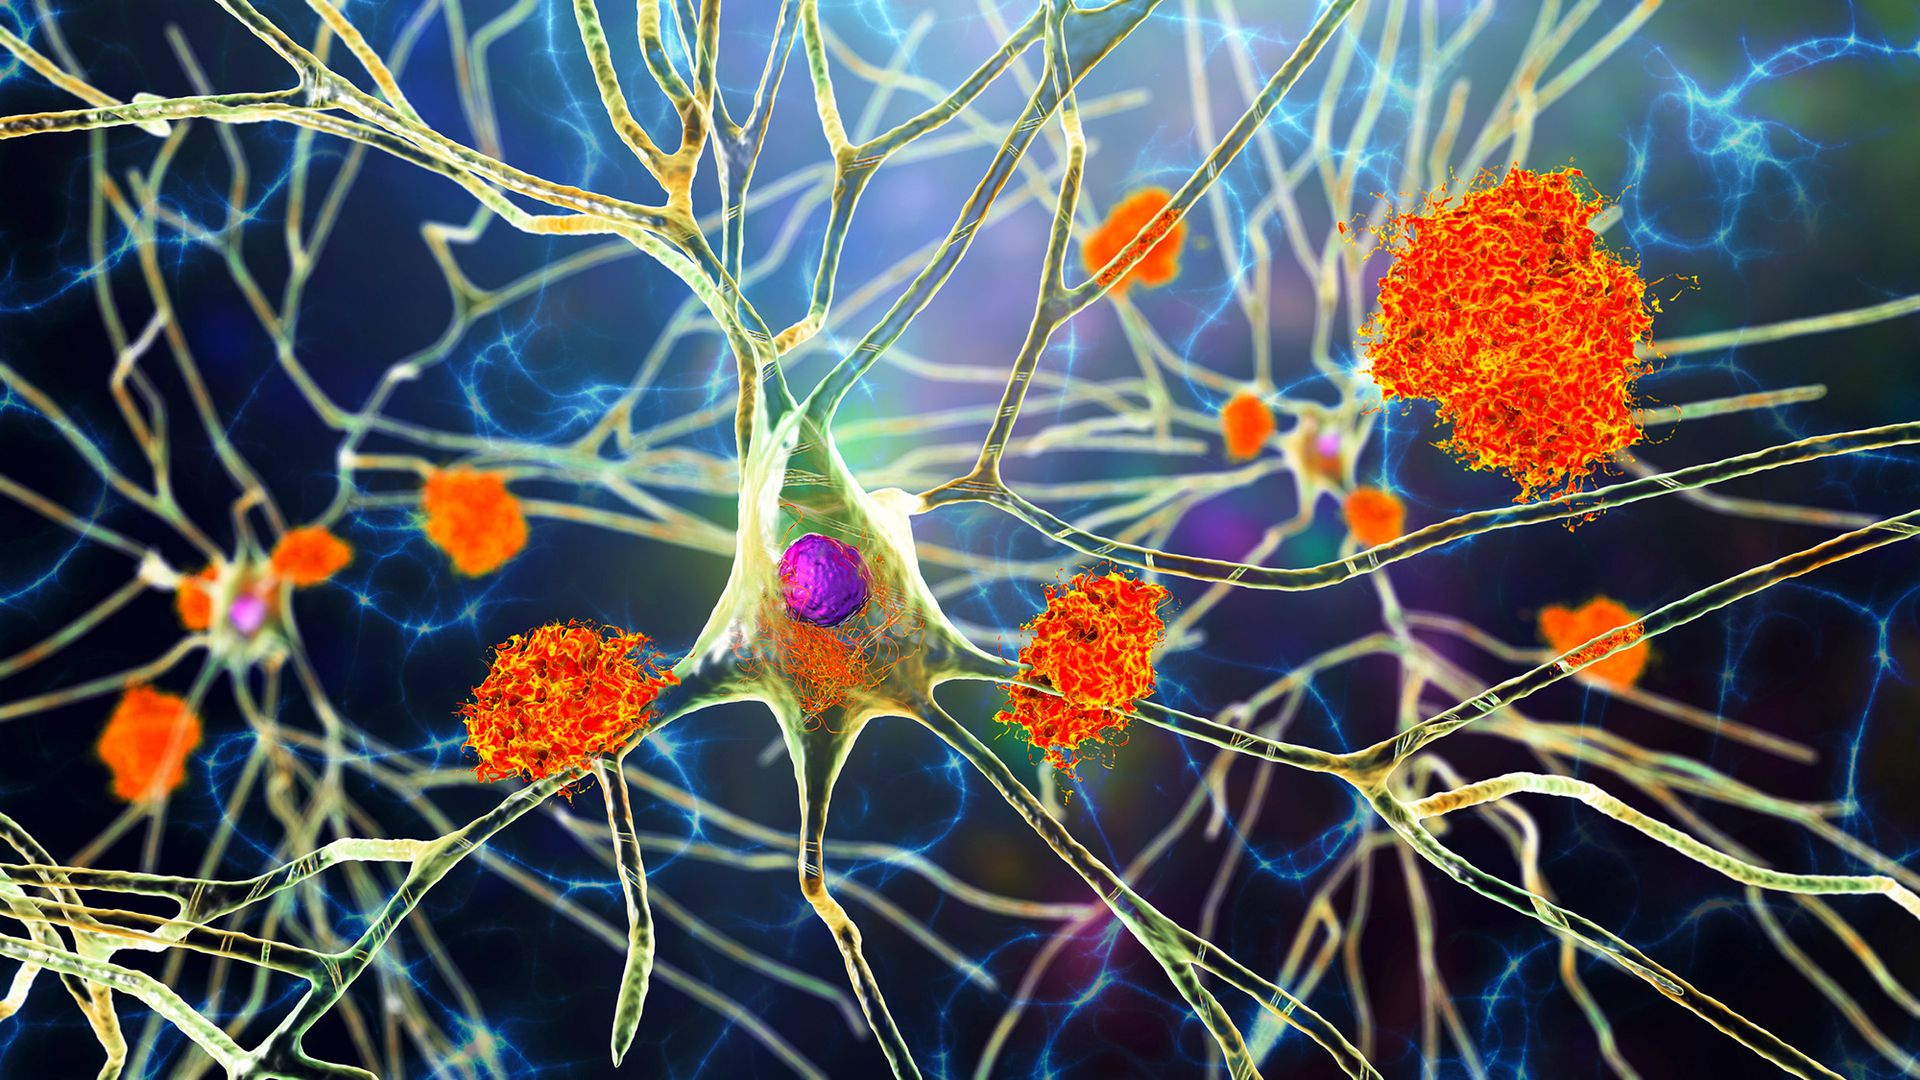
Laboratory data suggest that estrogen may help prevent the formation and accumulation of abnormal proteins that are related to Alzheimer's. (Image credit: KATERYNA KON/SCIENCE PHOTO LIBRARY via Getty Images)
Estrogen-only HRT was also tied to better clinical outcomes: Treated women were less likely to be diagnosed with dementia, were less likely to show clinical and functional cognitive decline, and had better scores on memory tests, on average, compared with untreated women. These findings drew on two large, separate groups of older women, reporting data from 21,400 people in total, but they didn't include data on when each woman started HRT.
Whereas earlier studies of HRT and dementia risk relied on doctors' ratings of patients' symptoms, the Neurology study measured levels of Alzheimer's-related proteins in the brain after death. That's a more "definitive" marker of disease, said Bruno, a co-author of the study. However, the research was observational, so it can't say whether estrogen-only HRT directly causes the better brain outcomes the team observed, she stressed.
Although the Neurology study's findings are promising, they don't necessarily match the results of other studies of estrogen-only HRT and dementia. For example, a slightly larger observational study, published in 2023, found that estrogen-only HRT was associated with an increased dementia rate.
In that research, most of the women took a type of estrogen called estradiol, while Bruno's study included a greater variety of estrogens. That may have been the difference in the two studies' results, but teasing that out would require further study. Meanwhile, the conflicting findings muddy the waters of what estrogen-only HRT can do for brain health.
Does timing matter?
One big finding from the Women's Health Initiative study was that starting HRT — either estrogen-only or combined — after age 65 was associated with worse cognitive function and increased dementia risk, said Yuko Hara, director of aging and Alzheimer's prevention at the Alzheimer's Drug Discovery Foundation.
The same may not be true for people who start HRT earlier. For context, menopause starts around age 51 to 52, on average, and it's preceded by perimenopause, a transitional period when hormone levels begin to drop, typically around the mid-40s.
An observational study published in August in the journal Alzheimer's & Dementia found that starting HRT between ages 46 and 56 was linked to a reduced risk of dementia. That study did not differentiate between estrogen-only and combined treatment; it lumped all of the data together.
Patches (pictured) are one form of systemic HRT. They deliver hormones through the skin and into the bloodstream. (Image credit: SVPhilon via Getty Images)
The protective link was especially strong in three groups: women with "surgical menopause," triggered by the removal of one or both ovaries; carriers of a certain variant of a gene called APOE that raises Alzheimer's risk; and women who had a relatively short time between their first period and menopause.
When it comes to using hormone replacement to protect brain health, the evidence isn't yet strong enough to recommend any kind of HRT as a way to protect the brain in all women, Hara said. Women who had one or both of their ovaries surgically removed are the exception to this rule.
"This is a distinct clinical population because the procedure can cause an abrupt, early loss of estrogen, rather than the gradual hormonal decline that occurs with natural menopause," Hara said.
For most women who have gone through natural menopause, "there is not enough evidence to recommend [HRT] specifically for preventing cognitive decline or dementia," she said.
HRT is not currently prescribed to prevent dementia — it is prescribed to ease menopause symptoms, such as hot flashes, night sweats and sleep disturbances. To settle the science on HRT and the brain, what's really needed is a well-designed clinical trial that follows women from perimenopause to postmenopause, Bruno said. That would reveal the effects of HRT on brain health and dementia risk more reliably than the studies done so far.
This article is for informational purposes only and is not meant to offer medical advice.
Artificial intelligence (AI) algorithms that hunt for cancer may do a better job when they approach the analysis as if they were a human pathologist, a new study suggests.
Many AI systems analyze preselected regions of a tissue sample, or they split a whole pathology slide into patches of a fixed size. By contrast, a pathologist searches more dynamically, panning across the tissue, zooming in and out, and pausing over areas that raise red flags. A whole slide can contain billions of pixels, while the evidence of cancer may occupy only a tiny patch.
Study co-author Zhi Huang, an assistant professor of pathology and laboratory medicine at the University of Pennsylvania, compared the process to a search-and-rescue helicopter. "You don't start by inspecting one square meter of ground," Huang told Live Science. You scan the landscape first and then swoop in for a closer look.
In the new study, published in July in the journal Nature, Huang and colleagues demonstrated that cancer-detecting AI might work better when it takes this humanized approach.
Training AI to hunt for cancer
AI algorithms called vision language models (VLMs) struggle with the first step that Huang described — that initial, cursory scan. That's in part because many pathology AI systems learn from what pathologists leave behind at the end of that search: a labeled image pointing out where the cancer is or an official diagnosis.
Instead, the researchers trained their new AI on pathologists' search behavior. They called this approach to training "Pathology-CoT," short for "chain of thought." It turns observable actions, including where pathologists move around and zoom in on an image, into training data.
To collect the data, the team created a tool that recorded how pathologists moved around a slide and changed magnification. The raw logs, gathered from eight pathologists, were messy, as a given pathologist might drift across a slide, overshoot their intended region of focus or fiddle with magnification to adjust it to their liking.
To clean up the data, the researchers filtered out those incidental movements, focusing on moments that appeared to represent deliberate attention, such as lingering over one view or making a sustained pan. Then, they compared those regions with eye-tracking data to check that the software was capturing where pathologists were actually looking.
For each region a pathologist inspected, the VLM also drafted a short rationale explaining why the region was worth examining and what features were visible; human pathologists could then accept, edit, or reject the rationale, creating additional training data for the AI. In one example, the AI flagged a portion of a slide as potentially metastatic and suggested zooming in to look for atypical cells. Other inspected regions were flagged as healthy tissue.
Ultimately, the researchers used this training method to build a new tool called Pathology-o3. It scans a slide at low resolution, uses a model trained on pathologists' behavior to choose regions worth a closer look, then sends higher-resolution views of those regions to a VLM for analysis.
Pathology-CoT trains algorithms to scan over a whole slide and then return to regions of interest for a closer look. (Image credit: Universal Images Group via Getty Images)
Putting it to the test
Huang said the goal of the new study was not to show that Pathology-o3 worked better than specialized AI models that are specifically built to detect specific types of cancer; those models are often trained disease by disease. Rather, the researchers wanted to see whether their new training approach could help a general-purpose AI navigate a pathology slide more effectively.
They compared Pathology-o3 to other general-use AI systems, such as OpenAI's o3, and asked the algorithms to examine slides containing lymph node tissue. These slides were collected from colorectal cancer cases and some contained metastatic cancer, which human pathologists had already labeled.
The algorithm correctly identified slides that were positive for cancer 100% of the time. However, of the slides it identified as positive, 15.5% were actually negative. By comparison, OpenAI o3 correctly identified slides that were positive for cancer 87.5% of the time. Of the slides it identified as positive, 53.3% were actually negative.
The researchers designed Pathology-o3 to err on the side of flagging something for another look, rather than potentially missing cancer. That might help to explain the rate of false positives, Huang said.
Whether that rate of false alarms is acceptable depends on how Pathology-o3 is used, said Mohammad Asadi, a data scientist at Stanford University who was not involved in the research. It's not precise enough for the AI to diagnose patients on its own, but it could still be useful for a system to point a human toward regions of a slide that are worth double-checking. It may be an advantage that the approach shows the pathologist a specific region to inspect rather than declaring an entire slide suspicious, he said.
The researchers tried repeating the test on an independent dataset that the algorithms hadn't seen before to see how well it worked on unfamiliar slides. Pathology-o3 correctly identified slides that were positive for cancer 97.6% of the time. Of the slides it identified as positive, 37.1% were actually negative. The finding is an example of how AI performance can change when the data source changes, even when the medical task stays the same.
Asadi explained this result suggests the system can still work with slides from a different source. But that result does not yet show that using this tool would make pathologists more accurate or efficient in practice.
Can it help pathologists?
The researchers applied their training approach to several existing VLMs, finding that the models' performance consistently improved after the training. That suggests that the navigation data from pathologists was useful across settings, Asadi said.
For Huang, that is the most important result. "The takeaway isn't our system," he said. "It's that the missing ingredient has been sitting in hospitals this whole time."
The study did not compare Pathology-o3 directly with human pathologists, but the researchers said that wasn't their aim.
"The right question isn't whether it beats a pathologist," Huang said. "It's whether a pathologist working with it catches more [cancer cases] and works faster." The current study did not address the latter question, either, but the team's next experiment is designed to test pathologists on the same cases with and without Pathology-o3, measuring what they catch and how long they take to do so.
The system's most plausible use is as a prescreening tool, Asadi said, but he stressed that the research has not yet shown that doctors who use it become faster or more accurate. Asadi wants an even tougher test: trials conducted across multiple hospitals that measure not just accuracy and speed but also pathologists' workloads. He wants the trails to assess the burden of false alarms from the AI algorithms and whether doctors recognize when the AI is wrong.
Importantly, cancer diagnoses can require information from multiple slides, stains and a patient's medical history, while the current system just reads one slide at a time. "I wouldn't claim it should diagnose on its own," Huang said.
This article is for informational purposes only and is not meant to offer medical advice.

 Login