❌

Normal view

New Scale Reveals How Culture Shapes What We Call Child Abuse

11 October 2026 at 09:09

Where is the line between firm discipline and child abuse? For millions of families in the United States, the answer depends on where they grew up, what their parents did, and how their culture defines good parenting. A new study published in the Journal of Child and Family Studies tackles this thorny question with an ambitious goal: building a scientific instrument that can measure how people from different backgrounds judge parenting practices that are accepted in some communities but condemned in others. The Parenting Practices and Discipline Scale, or PPDS, developed by Kevin Ortiz Diaz, Maureen C. Kenny, and Helia Baez at Florida International University, is one of the first tools designed specifically to capture culturally situated discipline practices that existing measures simply ignore.

The stakes are enormous. Child abuse is recognized as a global health issue, and in the United States it occurs at what researchers describe as epidemic proportions. Federal data show 546,159 victims of child abuse and neglect in 2023 alone, and the vast majority of these cases, roughly 89 percent, are committed by one or both parents. Children from minority groups are often the most affected, with Black or African American children among the most likely to experience abuse, second only to American Indian or Alaska Native children. Yet the definitions of what constitutes abuse vary dramatically across countries and cultures, creating a legal and ethical minefield for immigrant families who may not realize that practices considered normal at home are illegal in their new country.

The problem is particularly acute for Hispanic families, who make up 19 percent of the American population and represent the largest share of recent immigrants. Hispanic culture is far from monolithic, encompassing communities from South and Central America and the Caribbean with distinct traditions, but certain common threads run through the research. The concept of familismo, a cultural orientation and sense of obligation to family, has been linked to greater parental warmth in some studies. At the same time, physical violence as a disciplinary method remains common in many Hispanic cultures, and the chances that such behaviors are carried over by families immigrating to the United States are high. The result is a potential collision between generations of cultural practice and a legal system, anchored by the Child Abuse Prevention and Treatment Act of 1974, that defines abuse in terms of serious physical or emotional harm.

What makes the new study distinctive is its grounding in intersectionality theory, a framework rooted in feminist scholarship that examines how multiple categories of identity, such as race, ethnicity, gender, and nativity, interact to shape experience. Rather than treating demographic characteristics as independent variables, the researchers designed their analyses to test whether these dimensions jointly predict how individuals classify discipline practices as culturally acceptable or abusive. The framework has practical urgency: racial and ethnic disparities exist in both the reporting and substantiation of child maltreatment, and current child protection policies can disproportionately affect women of color who use social services and face heightened surveillance and risk of reports to child protective services.

The scale itself emerged from a careful two-stage piloting process. First, four experienced mental health clinicians specializing in child abuse, with 10 to 20 years of experience each, reviewed a draft pool of 54 items describing parenting behaviors and case vignettes. Then ten first-generation Hispanic immigrants from a range of nationalities, including Puerto Rican, Cuban, Colombian, Mexican, Dominican, and Nicaraguan participants, examined the refined items and identified which behaviors they would associate with parents in their own cultures and whether they would label those behaviors abusive or acceptable. Consensus required agreement from at least 70 percent of the pilot group. Eighteen items survived, ten identified as culturally acceptable behaviors such as yelling, using the chancla, the slipper famously wielded in many Latino households, or letting a child sleep with parents, and eight identified as abusive behaviors such as spanking, leaving a child alone in a car, or forcing a child to bathe with an adult.

The main study recruited 1,477 undergraduates at a large Hispanic-Serving Institution in Miami, ultimately yielding an analytic sample of 1,089 participants after exclusions for failed attention checks, missing data, and groups too small for meaningful analysis. The final sample was 72.2 percent Hispanic, 16.3 percent non-Hispanic Black, and 11.6 percent non-Hispanic White, nearly 70 percent U.S.-born, and predominantly female at 88.8 percent. Participants rated each of the 18 behaviors on a three-point scale: not abusive, inappropriate but not abusive, or abusive. The choice of a college population was deliberate, since emerging adults are on the cusp of parenthood, attitudes at this life stage predict later parenting intentions, and parenting practices tend to be transmitted intergenerationally.

Psychometrically, the study unfolded in two parts. Study 1 established the scale’s initial properties using exploratory factor analysis with principal axis factoring and oblique rotation on a polychoric correlation matrix, an approach suited to the ordinal, non-normally distributed responses. The analysis supported a two-factor structure: Factor 1 captured discipline and psychological aggression, including spanking, yelling, the chancla, cursing, ignoring, comparing, fighting, and religion, while Factor 2 reflected neglect and physical endangerment, such as using drugs in front of a child, refusing treatment for illness, and allowing smoking. The two factors accounted for 29.5 percent of the variance and were moderately correlated. Internal consistency for the full 18-item measure was acceptable at a Cronbach’s alpha of 0.71, though the abusive subscale showed weaker reliability, a limitation the authors acknowledge candidly.

Study 2 then deployed regression models to test how demographic identities shaped perceptions, and the results were revealing. Gender and parental status emerged as the strongest and most consistent predictors: women and parents were significantly more likely to classify culturally acceptable practices as abusive. Among Hispanic participants, those not born in the United States were more likely than U.S.-born Hispanics to view behaviors like spanking as abusive, a finding that ran counter to the researchers’ hypothesis and suggests that acculturation may shift parenting beliefs toward American child protection norms. Across racial and ethnic groups, Hispanic participants were more likely than Black participants to classify culturally acceptable practices as abusive. Notably, for the more overtly harmful behaviors in Factor 2, parental status was the only significant predictor, suggesting broad agreement that neglecting a sick child or encouraging substance use transcends cultural and gendered expectations.

The effect sizes were small, with the models explaining roughly 1 to 6 percent of the variance, a reminder that unmeasured cultural and contextual factors account for most of the variation in how people judge discipline. Still, the patterns carry real implications for prevention. The authors suggest that father-focused education programs may be valuable, since men were less likely to identify physical discipline as harmful and may therefore be at greater risk of normalizing such practices. Culturally adapted interventions have already shown promise, from brief summer parent training programs benefiting Hispanic children to the multinational Triple P Positive Parenting Program, and the PPDS could help practitioners identify which disciplinary practices are perceived as acceptable within specific communities, allowing messaging to be tailored rather than uniform.

The researchers are careful to frame their findings as preliminary. The sample was heavily female and drawn from a single Miami institution in a minority-majority city, socioeconomic status was not assessed, and social desirability bias may have influenced responses to questions about parenting. The abusive subscale needs refinement, and future work should apply confirmatory factor analysis and measurement invariance testing across cultural groups. Yet the core contribution stands: a novel measure that captures culturally situated discipline practices invisible to existing tools like the Alabama Parenting Questionnaire or the Child Abuse Potential Inventory. As parenting practices pass from generation to generation and families cross borders into legal systems with different rules, understanding exactly how culture shapes perceptions of abuse may be the first step toward protecting children without criminalizing the traditions their parents brought with them.

Subject of Research: Development and validation of a scale measuring cultural perceptions of parenting and discipline practices

Article Title: Development and Validation of the Parenting Practices and Discipline Scale in an Ethnically Diverse Sample

Article References: Ortiz Diaz, K., Kenny, M. C., & Baez, H. (2026). Development and Validation of the Parenting Practices and Discipline Scale in an Ethnically Diverse Sample. Journal of Child and Family Studies. https://doi.org/10.1007/s10826-026-03370-6

Image Credits: AI Generated

DOI: 10.1007/s10826-026-03370-6

Keywords: child abuse, parenting practices, discipline, Hispanic families, intersectionality, psychometrics, scale development, cultural perceptions, child welfare, corporal punishment, acculturation, exploratory factor analysis

Could psilocybin treat brain injuries? Neuroscientist explains how psychedelics could fill a gap in head trauma care

3 October 2026 at 11:00

Could a psychedelic drug help the brain recover from mild injuries? New research suggests that psilocybin, the mind-bending ingredient in magic mushrooms, might protect the brain from the damage caused by minor head impacts.

Even mild head impacts that don't count as concussions can raise the risk of neurodegenerative disorders such as chronic traumatic encephalopathy (CTE), so finding an effective treatment for these blows could be useful for warding off debilitating conditions down the line.

The new research, published in the journal Communications Biology, included only lab rats, so there's more work to be done to translate the findings to humans. But the early results hint at a new application for psilocybin β€” a drug that's already been explored for a range of other conditions, including depression, PTSD and anorexia.

Live Science spoke with study co-author Argel Aguilar-Valles, an associate professor of neuroscience at Carleton University in Ontario, about the new study and how the research might eventually translate to treatments for repetitive head injuries.

Nicoletta Lanese: In this new study you focus on mild head trauma. Why does that minor level of injury still raise concern?

Argel Aguilar-Valles: This work was spearheaded by our collaborator, Dr. Craig Ferris at Northeastern University in Boston. The idea was to focus on the cumulative effect of those milder head hits, or injuries, that happen quite commonly; a lot of children and older adults can have repeated instances of these events of head trauma, and it doesn't necessarily lead to any immediate treatment or hospitalizations because they are considered fairly mild.

But over time, there's evidence that this can lead to cumulative and long-term effects that can affect the health outcomes of these individuals, particularly as we age. It's a risk factor for several forms of dementia. So the idea was to try to model this with a milder version of head injury [in lab rats].

So it's repeated β€” it's three hits β€” they're controlled, they're fairly mild. And they produce some alterations in the brain networks that are evident in using either MRI [which looks at the brain's structure] or functional MRI [which analyzes brain activity] analysis.

NL: So these are head impacts that don't come with the symptoms associated with concussions?

AAV: It's always difficult to compare [what a rat is experiencing] to what a human might experience, especially here. One good way to put it is that there's no loss of consciousness β€ͺ—‬ so in those instances where the hits happen but you don't black out.

an x ray of a skull with a portion highlighted in red

Mild head injuries can cause cumulative harm if a person experiences multiple over time, evidence suggests. (Image credit: Shutterstock)

NL: Is there anything available now to manage and treat these mild impacts?

AAV: Well, as far as I'm aware, there's not really an intervention. I've experienced this secondhand with my children. Sometimes, they will come back from school and then they [the teachers] say, "OK, they had a hit on the head; there's a bump, but they didn't lose consciousness or anything."

Then sometimes, you go to the doctor concerned and typically you're told, "OK, just keep them under observation." If there's no vomiting, nausea, if there was no loss of consciousness, typically they just send you home and say keep an eye. Put some ice on it. Maybe don't overexert yourself in the next few days β€” and that's about it.

There is no intervention β€” for instance, if we do this [treatment], it's going to prevent you from developing dementia 50 years down the line. There's obviously nothing like that, particularly when you have repeated instances and the effects are cumulative.

NL: What made psilocybin seem like a potentially promising treatment for head trauma?

AAV: My group specifically has had an interest in testing the ability of molecules collectively known as psychoplastogens. We didn't coin the term, but it basically refers to all of these drugs that produce these brain-plasticity effects [changes in the brain's structure and activity]. These include serotonergic psychedelics [such as psilocybin and LSD, which affect serotonin receptors], and also things like ketamine or even MDMA.

We observe changes in cultured neurons in response to these drugs, in terms of dendritic complexity and increased synaptic spine density [changes in neurons' incoming and outgoing wires]. And in vivo [in live animals], you also observe functional reorganization of networks. All of these drugs have the ability to trigger these mechanisms. They do it through different pharmacological targets, but they all converge on some of these plasticity effects.

There are deficits in this plasticity in psychiatric illnesses, but also, obviously, in neurological disorders and even neurodegenerative disorders, where these plasticity mechanisms are completely nonfunctional.

So, we wanted to test the limit of the ability of these molecules to rescue, or to provide some therapeutic relief, in conditions where you have physical damage or neurodegenerative pathological mechanisms underlying the disorders. We observed β€” and not only us, but several other labs have also observed β€” that some of these molecules do seem to provide some level of therapeutic relief. [Editor's note: The current study looked only at physical trauma, but other labs have started to explore psilocybin for neurodegenerative disorders.]

It's still unclear if they're disease-modifying, in the sense they could provide lasting changes that can modify the course of the disorder. But so far, the evidence indicates that they can at least help to ameliorate some of the negative consequences of either neurodegeneration models or physical trauma, like in this case.

We don't know the limits of these drugs yet. I'm not trying to imply that they don't have limits; what I'm trying to say is that our knowledge is incomplete.

NL: Psychedelics have been more thoroughly studied for conditions like depression. In both depression and head trauma, could similar mechanisms explain the drug's potential benefits?

AAV: Some of the cellular effects might be similar. But the underlying condition can look quite different. Even if you think of two cases of depression, they can look very, very different. The drugs are going to be engaging similar mechanisms, but also the context in which these mechanisms are occurring will probably affect the outcome. What is remarkable about these drugs is that they seem to be working in both cases, so they're certainly tackling something that might be common in both situations.

We don't know the limits of these drugs yet. I'm not trying to imply that they don't have limits; what I'm trying to say is that our knowledge is incomplete. We don't know when they will work better than other potential treatment options.

I feel that will come when their clinical use is more widespread and we have a better idea of how they work in the heterogeneous populations that clinicians have in real life. In our animal models, conditions are very, very controlled and homogeneous, so they respond in a certain, similar way, whereas in the clinic, you observe huge disparity [in responses].

NL: Is there reason to think that psilocybin would be more promising than other psychoplastogens?

AAV: I think a lot of the focus on psilocybin has been because it's one of the psychedelics that's been more widely tested both in clinic and preclinical settings.

I'm not a clinician, but one of the reasons why psilocybin is favored over others is the length of the psychedelic trip. It's a few hours. If you go with something like LSD, it will last much longer. While the person is under the influence of the drug and undergoing the trip, there needs to be clinical supervision, so it becomes really challenging logistically to arrange sessions with psychedelics that last a long time.

That's also motivated preclinical research, like ours, to focus on this drug, as opposed to others that may have similar effects. From a potential translational perspective, it might be a safer bet to study this drug.

NL: In clinical trials of psychedelics, scientists often use a very small dose to try to avoid triggering strong hallucinogenic effects. Was that a goal with the rats?

AAV: No, they're probably experiencing something β€” this is a relatively high dose. A lot of people use 1 milligram of psilocybin per kilogram of body weight. In this case, they were using 3 milligram per kilogram, and it was based on previous imaging studies where they looked at the effects of this drug.

One measure we use is the "head twitch response," which is a behavioral measure that we commonly use in rodent work to test the hallucinogenic potential of a drug. This is a very rapid head movement that occurs in response to the serotonergic psychedelics. It's a behavioral response that correlates with hallucinogenic potential, and not perfectly.

For psilocybin, it's been very well characterized in the sense that it's mediated by the serotonin 5-HT2A receptor [in rodents], which is the same receptor that mediates hallucinations and the psychedelic trip in humans.

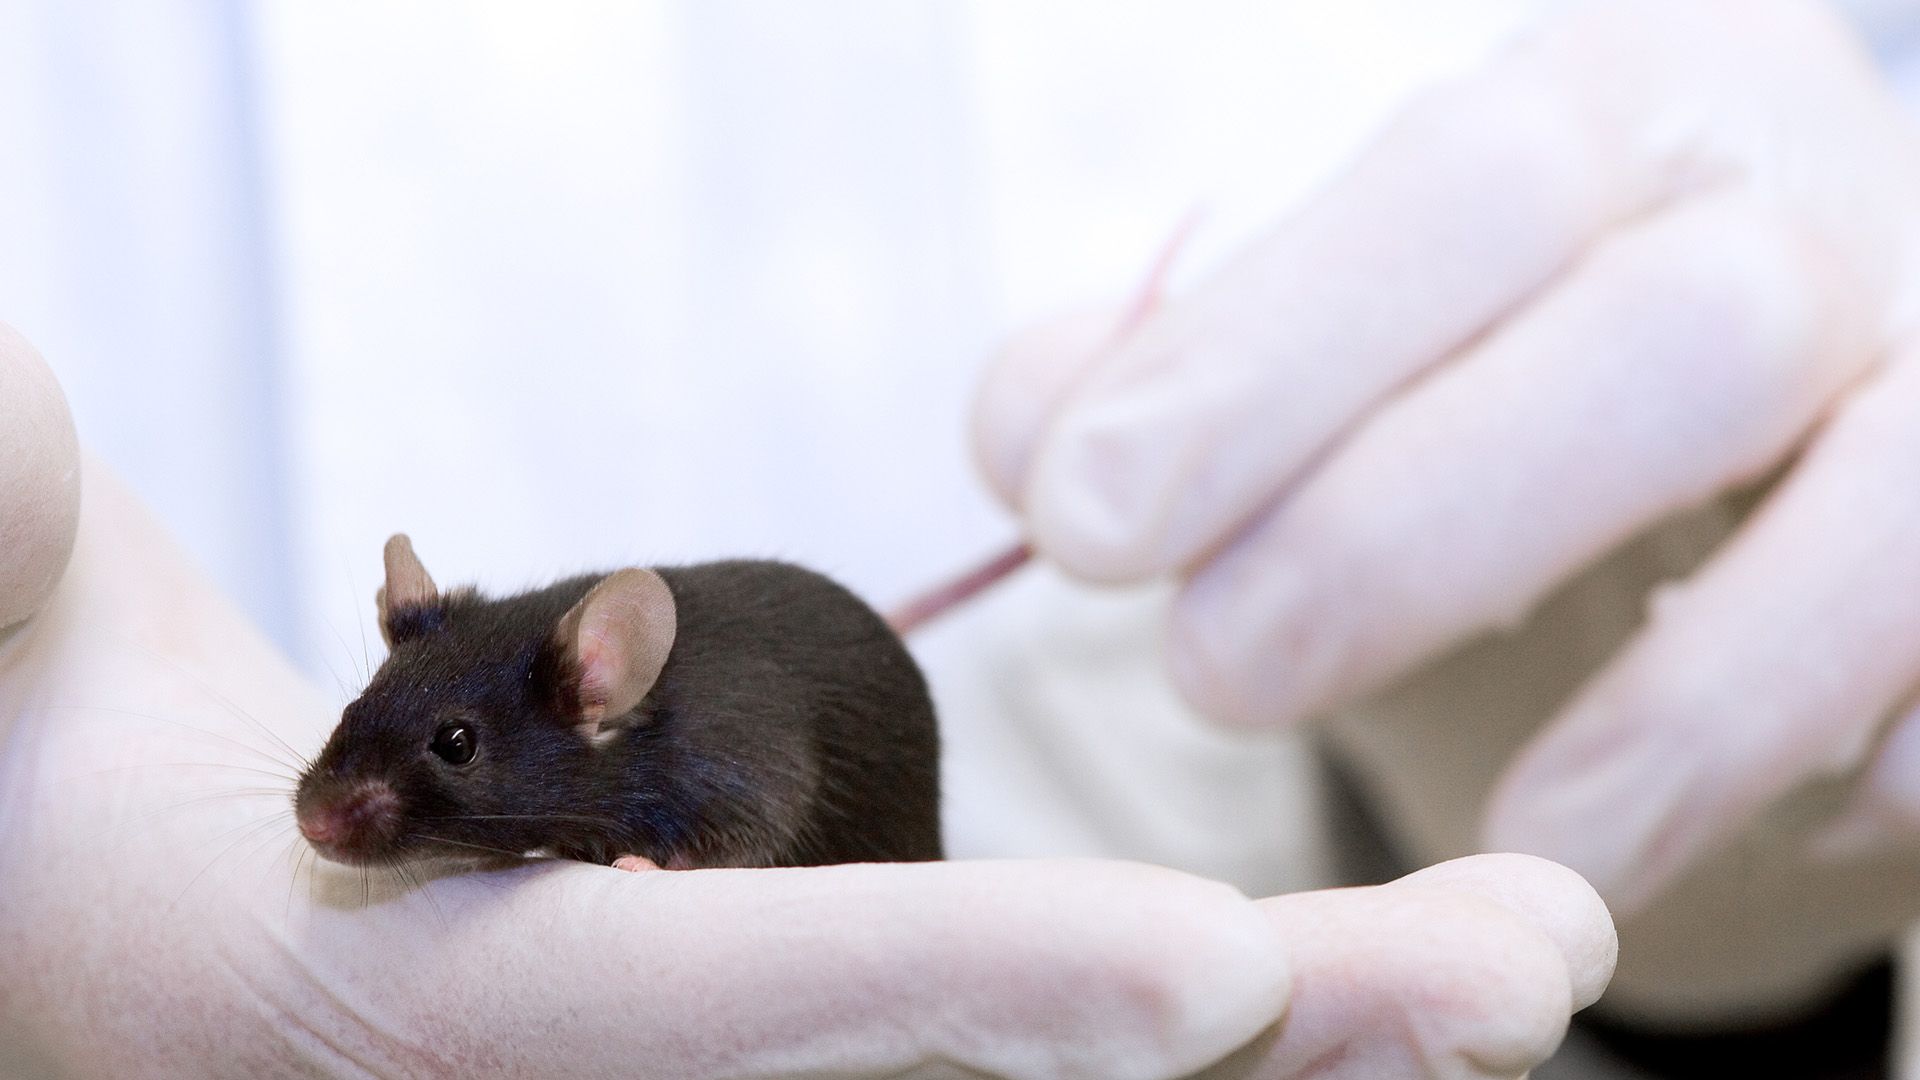
A small brown mouse sits in the palm of two white gloved hands.

The new study that Aguilar-Valles co-authored looked only at rats. More work is needed to understand if psilocybin could be useful for humans with head injuries. (Image credit: dra_schwartz via Getty Images)

NL: What notable changes did you see in the rats in this study?

AAV: The measurements were done nearly three weeks after the injury. It's relatively short if you think of a human, but for a mouse, things happen much faster metabolically and physiologically. There was at least evidence of increased phosphorylation of tau [changes in a specific brain protein tied to Alzheimer's], and that was reversed by the treatment with psilocybin. That was certainly one surprising finding, and it's worth following up, I believe.

But also the hyperconnectivity β€” the brain's functional connectivity was really dramatically affected in the treated rodents with the head hits. They not only recovered but went to higher levels than the control-group animals.

We don't really know what the meaning of that is, but certainly it's quite remarkable how the networks became hyperconnected. And hopefully that means something positive for the animals. But it was certainly surprising, the level of recovery of that particular measure.

NL: And these effects were seen throughout the brain?

AAV: There were effects in a lot of brain regions β€” the thalamus, the hippocampus, the basal ganglia, and all different parts of the cortex, etc. One of the things that stands out from this study was the connectivity of dopaminergic nuclei [hubs of dopamine production in the middle of the brain]. Their connectivity is really fundamentally changed by the hits and then by the treatment with psilocybin.

These modulatory regions, the dopaminergic regions, are concentrated in one part of the brain, but they affect overall brain function because they have these widespread connections. So they're really crucial for a lot of functions, and we're seeing effects in these regions β€” that's really intriguing.

NL: Is it known whether the strength of the psychedelic trip has anything to do with the degree of benefit?

AAV: It is currently a hotly debated topic in the psychedelic field, whether the intensity of the psychedelic experience has anything to do with the beneficial effects or not. You can envision situations like psychological trauma, as opposed to physical trauma, where that trip might be part of the therapeutic mechanisms. It becomes evident in the debriefing sessions after psychedelic treatment, where it seems like in some cases, the psychedelic experience is fundamental.

But these are fairly correlative measures β€” if the two happen at the same time, it doesn't mean that they are linked together causally. So that's something that is being tested actively. One of the ways is the development of these non-hallucinogenic analogues that seemingly trigger similar plasticity mechanisms as their psychedelic counterparts do [without causing a trip].

I don't think we've had the first clinical trial with these drugs yet. Some of them may have undergone Phase I clinical trials just for safety, but I believe none of them have been tested in Phase II trials yet [in which their effectiveness is explored for specific conditions].

NL: Given this work is in rats, what are the next steps to translate this into a treatment for people?

AAV: Extending the observations, like other groups have done β€” looking at what happens if you do give this treatment months after the events. It's still unclear to me if, with this model we have, you will have effects months later.

We have some correlative measures that potentially BDNF expression [a gene for brain-derived neurotrophic factor, which helps neurons grow connections] is increased, and also the levels of its receptor, called TrkB. That is a possibility that needs to be further investigated, trying to find out whether these neurotrophic factors are crucial for the effects that we're seeing.

And obviously, the psychedelic trip is still a potential issue. But testing whether these non-hallucinogenic derivatives have the same lasting effects as their hallucinogenic counterparts do β€” that will be crucial and that can, in some cases, potentially facilitate the translation [into treatments]. Because not every person reacts the same way to these hallucinogenic compounds, and not everybody has the same risks.

NL: I assume the non-psychedelic options might be better for children, for instance?

AAV: We don't know what the consequences [of psychedelic use] are in a developing brain. There's not enough data. That will be obviously a big thing to sort out before recommending the use of these drugs, and maybe some of those non-hallucinogenic derivatives may hold the answer for that β€” for those cases where you really don't want to induce a full-on psychedelic experience.

There's also schizophrenia and a bunch of other psychiatric diagnoses with psychosis associated with them β€” from bipolar or psychosis-like events or episodes β€” where you might not want to apply a serotonergic psychedelic.

NL: Looking ahead to the next five to 10 years, what do you hope to see in the field?

AAV: There's a lot of enthusiasm in the field and a lot of push to try to characterize and understand better these drugs, from a basic perspective or a cellular level up to a brain wave level and then also the psychological effects. So there are a lot of different disciplines implicated in studying these drugs, and I think that's really exciting. That will hopefully lead to a wealth of knowledge about these drugs β€” not only their effects but also their limitations and their potential risks.

Hopefully we will have a balanced approach as scientists, to be able to really tease apart in which cases it [psychedelic treatment] will be really useful and in which cases the risks outweigh the benefits. That will be crucial to understand.

There's a lot of potential there, but we should proceed with caution.

This interview has been condensed and edited lightly for clarity. This article is for informational purposes only and is not meant to offer medical advice.

Help us improve Live Science Pro: We're always trying to make our content better. Leave us feedback about Pro here.

❌