❌

Reading view

Quote by Hannah Arendt: “Loneliness is not solitude. Solitude requires being alone whereas loneliness shows itself most sharply in company with others.”e: “He who has a why to live for can bear almost any how.”

Thought of the week, from Hannah Arendt: “Loneliness is not solitude. Solitude requires being alone whereas loneliness shows itself most sharply in company with others.”

We tend to treat those two words as different doses of the same medicine. Solitude is a bit alone, loneliness is very alone, and both come down to the simple business of not having people around. Arendt is saying something stranger and, I’ve come to believe, far truer. They aren’t two points on one scale at all. They’re separate states, and the proof is that the worst of one tends to strike at the exact moment you’re surrounded.

The two aren’t even related

Solitude is being alone, and it can be one of the better things in a life. When I’m in it, I’m not actually without company. I’ve got myself. There’s a quiet conversation that goes on between you and you when no one else is about, and in solitude that conversation has room to happen. You think, you wander, you settle. Alone, and entirely fine.

Loneliness is a different animal altogether. It’s the sense of not being met, of there being nobody, possibly including yourself, who registers that you’re really there. And its cruel signature, the thing Arendt puts her finger on, is that it doesn’t require you to be physically alone to do its work. It does its sharpest, coldest work in a full room.

Two evenings

I can hand you both states as two specific nights.

The first was a solitary one. An evening alone in my flat, no plans, nobody about, the phone face down. I cooked something slow, read for a good while, sat out on the balcony watching the city do its restless thing. Not a word exchanged with another human for hours, and I felt full, settled, perfectly good company to myself. That was solitude. Alone, and not lonely in the slightest.

The second was a crowded one. A big party here in Bangkok, packed and loud, a whole room of people I half-knew, a drink in my hand, laughter going off all around me. And somewhere in the thick of it, a cold wave of about the purest loneliness I know rolled straight through me. Surrounded on every side, and abandoned. Everyone present, nobody meeting me, the noise widening the gap rather than filling it. The strange thing was that I’d have sworn, walking in, that a big lively night was exactly what I needed. It turned out to be the precise opposite of the cure. I left early, walked home by myself, and felt better the instant I was out the door, because being alone had never been the problem. The un-meeting crowd was.

Why we reach for exactly the wrong cure

Because we muddle the two together, we reliably apply the wrong fix. Someone admits they’re lonely and we tell them to get out more, see people, fill the diary up. Sometimes that helps. Often it makes things worse, because we’ve prescribed company for a condition that sharpens in company. It’s handing a man dying of thirst a tall glass of saltwater. More people is the right answer to a solitude you didn’t choose. It is frequently no answer at all to loneliness, and now and then it’s an accelerant.

It runs the other way too. People who genuinely need solitude, real time alone with themselves, often grow frightened of it, because they’ve absorbed the idea that all aloneness is the dangerous kind. So they stuff their lives with company to dodge a thing that would actually have done them good, fleeing solitude as though it were loneliness, and losing the one dependably restorative sort of alone there is.

The company you keep with yourself

What sits underneath Arendt’s distinction is the relationship you have with your own self. In solitude you’re alone but not deserted, because you’re still keeping yourself company, still on decent terms with the only person guaranteed to be in the room. Loneliness, in her sense, is when even that company gives out, when you’ve been deserted by everyone else and, worse, by your own self too, and that is a desertion no crowd on earth can reach. A party can’t talk you out of it, because the party isn’t addressing the actual absence. Arendt put it with a precision I can’t improve on: in solitude I am with myself, two-in-one, but in loneliness I am truly one, left by everybody. The absence is closer to home than any room full of strangers.

That reframes the whole problem. If the loneliness that bites hardest in a crowd is partly the loss of your own company, then a real portion of the cure was never out there in a bigger guest list at all. It’s in rebuilding the ability to sit with yourself, so that you turn up to the party already in decent company, and the crowd becomes a bonus rather than a frantic, failing remedy. The people hardest to make lonely tend to be the ones most at home in their own solitude, the ones who never lost the thread of that quiet two-way conversation in the first place.

Working out which one you’re in

So the genuinely useful first move, when the alone feeling lands, is to figure out which of the two has actually arrived, because they want opposite things from you. If it’s solitude you’re flinching from, the answer is to stop bolting, sit in it, and rediscover that your own company isn’t an enemy to be drowned out. If it’s loneliness, especially the sort that flares up in a crowd, the answer was never simply more bodies in the room. It’s the harder work of being properly met by a few people, and of repairing the relationship with the self that’s gone silent.

I think about those two evenings whenever I catch myself reaching for company as a cure-all. The night alone that felt full, and the crowded night that felt like being left behind. Between them they taught me what Arendt put far more elegantly, that being alone and being lonely have almost nothing to do with one another, and that the loneliest I am ever likely to be is not in an empty flat but in a bright, loud room full of people, not one of whom, myself included, is fully there. Solitude I can always go home to. Loneliness is the thing that follows me into the party. Telling them apart is the first step to not handing myself the saltwater every time.

The post Quote by Hannah Arendt: “Loneliness is not solitude. Solitude requires being alone whereas loneliness shows itself most sharply in company with others.”e: “He who has a why to live for can bear almost any how.” appeared first on Space Daily.

  •  

Quote by Friedrich Nietzsche: “He who has a why to live for can bear almost any how.”

Quote of the day, from Friedrich Nietzsche: “He who has a why to live for can bear almost any how.”

It’s the kind of line that can sound like a fridge magnet if you meet it cold, the sort of thing printed under a photo of a mountain. But it has a much heavier history than the mountain photo suggests. Viktor Frankl, the psychiatrist who survived the Nazi camps, took this exact sentence as the key to who lived and who didn’t around him. The prisoners who held on, he observed, were rarely the strongest or the best fed. They were the ones who still had a why, a person to get back to, a piece of work unfinished, some reason waiting on the far side. Strip a man of his why and the how, however mild, became unbearable. Give him one and he could endure almost anything.

The how is never the deciding factor

We get this backwards most of the time. We assume people break under the weight of their circumstances, the how, and that if we could just make the how easier, lighter, more comfortable, people would cope better. So we chase comfort, and we treat hardship as the enemy, and we measure a good life largely by how few difficult hows it contains.

What Nietzsche saw, and Frankl confirmed in the most extreme laboratory imaginable, is that the how is almost never what does people in. People endure staggering hows, illness, grief, poverty, loss, as long as the why holds. And people crumble under remarkably gentle hows, a comfortable life, no real hardship at all, the moment the why goes missing. It isn’t the size of the burden that breaks a person. It’s carrying any burden at all without a reason to.

My grandmother, who refused to die on schedule

I watched this play out in my grandmother, my mum’s mother, in the last stretch of her life.

She’d been given a grim prognosis, a matter of a few months at the outside, and by every medical expectation she should have gone roughly when they said she would. She did not. She hung on, stubbornly, well past the date, and the doctors did that polite shrug doctors do when a patient ignores the timetable. What kept her going wasn’t medicine or clean living or luck. It was my cousin’s wedding, eight months out, which she had decided, flatly and without negotiation, that she would attend.

That wedding was her why. She talked about it constantly, planned her outfit, fussed about the seating, used it as a rope to pull herself along a corridor everyone else assumed she’d already reached the end of. She made it. She sat in the second row in a hat she’d agonised over for weeks, cried through the vows, danced one slow number with my cousin, and she died about three weeks later, the job done, the why spent. I have never seen a clearer demonstration that the body will keep going far past what seems possible if the mind has somewhere it absolutely intends to be.

The danger of a borrowed why

The trouble with a why is that not all of them hold, and we’re often running on ones that can be taken away. A why pinned entirely to another person, to your children, say, or a partner, is real and powerful, but it has a hostage quality. If they leave, or grow up, or die, the why goes with them, and people who built their entire reason for being on a single relationship can collapse spectacularly when it ends.

The sturdiest whys, I’ve come to think, tend to be the ones that renew themselves. A piece of work that’s never quite finished. A craft you keep getting better at. A cause larger than your own lifespan. Even, in my grandmother’s case, a next thing, always a next thing, a wedding and then a christening and then a great-grandchild she’d decided in advance she had to meet. She kept manufacturing new whys the moment the old ones were used up, which is, I suspect, the real trick. A why isn’t a thing you find once and keep. It’s a thing you have to keep renewing, because life keeps spending them.

Why comfort can be the quiet danger

What unsettles me about all this, as a reasonably comfortable man living a reasonably comfortable life, is the warning Nietzsche’s line carries underneath. If a why lets you bear almost any how, then the people most at risk aren’t necessarily the ones with the hardest hows. They’re the ones with the emptiest whys.

You can build a life with the difficulty engineered almost entirely out of it, smooth, cushioned, frictionless, and find yourself strangely unable to bear it, because comfort is not a why. It’s just an easy how. A person with everything and no reason can be far more fragile than a person with nothing and a fierce one. Which means the modern project of removing all hardship, if it isn’t matched by the harder work of building a reason, can leave people more breakable, not less. We optimise the how and forget to ask about the why, and then wonder why so many of the comfortable are the ones falling apart behind closed doors.

The question worth keeping in view

I don’t have my grandmother’s clarity. Most of us don’t, until something forces it on us. But the quote has changed the question I ask myself when a stretch of life gets heavy. The instinct is always to ask how do I make this easier, how do I reduce the load, how do I escape the how. Nietzsche points at the better question, which is whether the why is still there at all.

Because if the how feels unbearable, it’s worth checking whether the real problem is the weight or the missing reason underneath it. Often the burden hasn’t actually grown. The why has slipped out from under it, and the same load that was fine last year has become impossible, not because it got heavier, but because the thing that made it worth carrying went missing while you weren’t looking.

My grandmother couldn’t be killed on schedule because she point-blank refused to miss that wedding. None of us gets to choose our hows, not really. The one thing we have any say over is whether we’ve got a why strong enough to drag us through them, and whether, when one gets used up, we’re paying enough attention to reach for the next.

The post Quote by Friedrich Nietzsche: “He who has a why to live for can bear almost any how.” appeared first on Space Daily.

  •  

Across more than 100 countries, researchers have documented a “U-curve” of human happiness — life satisfaction reliably dips through middle age before rising again in late life — and the happiness people report in their late 60s and 70s is often greater than what they felt in their 30s, in a quiet curve almost nobody expects to be on while they are inside the dip

If you are currently in your mid-forties and feeling somewhat worse about your life than you remember feeling in your twenties, the data suggest you are not alone, you are not broken, and the curve you are on bends back upward. The basic finding is one of the more robust patterns in the empirical economics of well-being. In a long series of papers running from approximately 2004 through 2025, the economists David Blanchflower of Dartmouth College and Andrew Oswald of the University of Warwick have analysed survey data on life satisfaction and happiness from millions of individuals across more than 130 countries. The pattern that has consistently emerged is a U-shape — high in youth, declining through early and middle adulthood, reaching a minimum somewhere in the late forties, and then rising again through the late fifties, sixties, and into the seventies. The same shape appears, with minor variations, in advanced economies, developing economies, individual US states, every European country examined, and the great majority of Latin American, African, and Asian countries surveyed.

The most comprehensive single statement of the finding came in 2020, when Blanchflower published a National Bureau of Economic Research working paper analysing life-satisfaction data from 132 countries. Averaging across the country-level estimates, he found the age minimum of well-being at 47.2 years in advanced countries and 48.2 years in developing countries — strikingly similar figures across radically different economic and cultural contexts. “The happiness curve is everywhere,” he concluded. A 2021 follow-up in the Journal of Population Economics extended the analysis to 145 countries and confirmed the same essential pattern, with the U-shape robust to statistical controls for income, education, marital status, and employment.

What the data actually show

The shape of the curve, examined country by country, is not identical everywhere. In some countries the dip is sharper; in others it is more gradual. The recovery phase varies in steepness. The absolute level of happiness at any given age varies enormously across countries — Scandinavian populations report substantially higher life satisfaction at all ages than populations in many lower-income or politically unstable countries. But the basic temporal pattern — that any given country’s well-being levels are lower in midlife than in either young adulthood or old age — replicates across an extraordinary range of national contexts. As reported in the University of Warwick’s press coverage of the original 2008 Blanchflower-Oswald paper, the researchers found the same U-shape in happiness levels and life satisfaction across 72 countries in their initial dataset, including economies as different as Norway, China, Iraq, and Argentina. The pattern is not specific to wealthy industrial democracies or to any particular cultural tradition. It appears to be a feature of being human across the adult lifespan, regardless of where the human in question happens to live.

For people inside the dip, the data carries a specific implication. The years between approximately 40 and 55 are, on average across the surveyed populations, the lowest-satisfaction years of adult life. The recovery is not automatic and not guaranteed for any individual — these are statistical averages across enormous populations, and any given person can defy the curve in either direction. But the general trajectory means that the experience of feeling that life has somehow narrowed or dimmed in midlife is, by the available data, the modal experience for adults in this age range, not a personal failure or a sign that something has specifically gone wrong. The corollary is that the late sixties and seventies, contrary to widely-held assumptions about ageing as a steady downhill, are typically reported by the people living through them as among the higher-satisfaction periods of adult life.

Why the curve might exist

The mechanisms behind the U-shape are not fully settled, and several competing explanations are now under active research. One leading hypothesis comes from the socioemotional selectivity theory developed by the Stanford psychologist Laura Carstensen, which proposes that as people perceive their remaining time as shorter, they progressively prioritise emotionally meaningful experiences over information-seeking or status-seeking ones. Older adults, in this account, are happier in part because they have become better at selecting the activities, relationships, and goals that actually produce contentment, and at letting go of the ones that do not. A second hypothesis emphasises expectation adjustment — by the late forties, most adults have learned what their lives will and will not deliver, and the gap between what they hoped for and what they have can produce acute disappointment; by the late sixties, that gap has often been reconciled. A third hypothesis emphasises the practical reduction of midlife stressors — the children grown, the career trajectory settled, the financial pressure typically eased — which simply removes some of the load that was depressing midlife well-being.

Per a 2022 review and replication of the U-curve in Frontiers in Psychology, neurobiological mechanisms may also play a role. Midlife is the period when adults typically carry the heaviest combination of work, financial, caregiving, and intergenerational responsibilities — the “sandwich generation” effect of being responsible for both children and ageing parents simultaneously. The cumulative allostatic load of chronic stress can suppress subjective well-being for years at a time. As these responsibilities reduce in late life, the stress load reduces, and the underlying capacity for satisfaction reasserts itself.

What the framework does not claim

Intellectual honesty requires noting that the U-curve finding has been actively contested within happiness economics over the past two decades, and the methodological debate remains unresolved on several points. Some critics — notably Paul Frijters and Tony Beatton in 2012, and Sonja Kassenboehmer and John Haisken-DeNew in 2013 — have argued that the U-shape appears in cross-sectional data but weakens substantially or disappears in longitudinal data that follows the same individuals across their lives. Others have suggested that the U-shape may be partly an artifact of cohort effects (different generations having different baseline happiness levels) rather than a pure age effect. The Princeton economist Angus Deaton has argued that the U-shape may depend on specific socioeconomic conditions and may not be as universal as the Blanchflower-Oswald papers suggest.

The Blanchflower group has responded to these critiques with subsequent analyses that they argue confirm the basic pattern across multiple datasets and methodological approaches. The debate continues. What is largely uncontested is that the well-being of younger adults (ages 18-25), particularly young women, has declined substantially in many developed countries since approximately 2014, in ways that complicate the traditional U-curve picture for the most recent cohorts. As documented by the Global Interdependence Center in a 2025 review of the global U-shape literature, the youth-end of the curve has flattened or reversed in some recent samples — meaning that for some current young adults, the typical pattern of starting high and dipping into midlife may not apply to them in the way it did to earlier generations. The midlife dip and the late-life recovery, however, continue to show up consistently in the older portions of the data.

Why the curve is invisible while you are on it

The most disconcerting feature of the U-curve, for people currently inside the dip, is that it tends to be undetectable as a temporary pattern from within. Someone in the middle of midlife dissatisfaction typically experiences the dissatisfaction not as one particular point on a long curve but as the new permanent reality of being themselves. The retrospective view from the seventies — that the forties were, statistically speaking, the lowest-satisfaction years of an otherwise broadly improving life — is not available to the person in their forties, who has no way to see the forthcoming recovery. The curve appears in the aggregate data because researchers can examine millions of lives at different ages simultaneously. Each individual life sees only the slice it is currently in. The empirical contribution of the Blanchflower-Oswald research programme, whatever the eventual outcome of the methodological debates around it, has been to make the broader shape visible at all — to point out, on the basis of survey data from hundreds of millions of human beings, that the dip is a feature rather than a final destination, and that the curve generally bends upward again on the other side.

The post Across more than 100 countries, researchers have documented a “U-curve” of human happiness — life satisfaction reliably dips through middle age before rising again in late life — and the happiness people report in their late 60s and 70s is often greater than what they felt in their 30s, in a quiet curve almost nobody expects to be on while they are inside the dip appeared first on Space Daily.

  •  

The Stoic philosopher Epictetus taught that almost all human suffering comes from confusing the things we can control with the things we cannot — and the simple practice he proposed, of separating those two categories every morning before anything else, has quietly become the foundation of modern cognitive behavioral therapy nearly two thousand years later

If you have ever lain awake at 3 a.m. running through a conversation you cannot rewrite, a decision someone else has already made, or a future event you cannot guarantee, you have arrived at the specific psychological territory that a former Roman slave named Epictetus mapped out approximately 1,900 years before you got there. Epictetus, who lived from roughly 50 to 135 CE, did not write anything down. His teachings were recorded by his student Arrian, who transcribed his lectures and later compiled the most essential ones into a short handbook called the Enchiridion. The handbook, approximately 53 short chapters long, opens with what is probably the single most consequential sentence in the entire Stoic tradition. According to the Stanford Encyclopedia of Philosophy’s entry on Epictetus, the line begins: “Of things that exist, some are in our power and some are not in our power. Those that are in our power are conception, choice, desire, aversion, and in a word, those things that are our own doing. Those that are not under our control are the body, property or possessions, reputation, positions of authority, and in a word, such things that are not our own doing.”

What Epictetus then argued is that almost all human suffering arises from a single, repeated, correctable error: confusing the first category with the second. We try to control things that belong in the not-in-our-power column — other people’s opinions of us, the behaviour of relatives, the outcome of negotiations, the weather, the economy, the past, the future, our own bodies and lifespans — and we neglect the small, genuinely controllable category, which consists of our own judgements, intentions, and responses. The result is chronic frustration about things we were never going to be able to change, accompanied by chronic neglect of the things we actually could change. The Stoic prescription, articulated in chapter 1 of the Enchiridion and elaborated across the much longer Discourses, is to perform this sorting deliberately and continuously, until it becomes second nature.

The dichotomy in practice

The classical Stoic exercises around what modern Stoic-revival writers have called the “dichotomy of control” were not abstract philosophical contemplations. They were daily practices, intended to be performed in the morning before the rest of the day’s events began, and reviewed in the evening after the day was over. The morning practice involved anticipating the day’s likely difficulties — encounters with rude or dishonest people, unexpected setbacks, frustrations of various kinds — and pre-sorting them into the two categories. The encounter with the rude colleague would happen or not happen; that was not in our control. Our response to it was. The traffic on the road would be heavy or light; that was not in our control. Our patience inside that traffic was. The clients we hoped to sign would sign or not sign; that was not in our control. Our preparation, our presentation, and our equanimity in the meeting were.

The same logic applied to the bigger questions of a life. Whether one’s children turn out as one hopes, whether one is loved by the people one loves, whether one’s career succeeds, whether one stays healthy, whether one lives to be old — Epictetus would have placed all of these squarely in the not-in-our-power column. The only things in our power, in his strict reading, are our own judgements and responses. As the modern Stoic writer Donald Robertson summarises the framework, drawing on Epictetus’s own emphasis: maintaining the distinction between what is up to us and what is not is the foundational practice from which all other Stoic exercises follow. Per Philosophy Break’s reference on the dichotomy of control as a Stoic device for a tranquil mind, the point of the practice was not resignation but reallocation of attention — moving one’s effort away from the controllable shape of the world and toward the controllable shape of one’s own response to whatever world arrives.

The route from Greece to the modern clinic

The connection between Epictetus’s teaching and modern cognitive behavioural therapy is not a strained academic parallel. It is direct, documented, and explicitly acknowledged by the founders of the therapeutic tradition themselves. As reported in a 2023 review in Neurological Sciences on the Western origins of mindfulness therapy in ancient Rome, Albert Ellis, the founder of Rational Emotive Behavior Therapy in 1955, explicitly credited Epictetus as the primary philosophical influence on his approach. Ellis quoted the famous line from chapter 5 of the Enchiridion — “Men are disturbed not by things, but by the views which they take of them” — in his foundational 1955 paper introducing the new therapeutic method, and reproduced it in numerous subsequent publications. Aaron Beck, who developed Cognitive Therapy in the 1960s (the broader framework that came to be called Cognitive Behavioural Therapy when combined with behavioural techniques), wrote in his original treatment manual for depression that “the philosophical origins of cognitive therapy can be traced back to the Stoic philosophers, particularly Epictetus.”

The structural parallels are precise. Ellis’s foundational ABC model — Activating event, Belief about the event, Consequence (emotional or behavioural) — maps almost exactly onto Epictetus’s distinction between events themselves and our judgements about events. The CBT technique of “cognitive restructuring,” which involves identifying automatic negative thoughts and examining whether they accurately reflect reality, is structurally identical to the Stoic exercise of examining one’s judgements about external events. The CBT concept of “locus of control” — directing attention toward what one can influence rather than what one cannot — is the dichotomy of control restated in the language of mid-twentieth-century psychology. Even the third-wave therapies like Acceptance and Commitment Therapy (ACT) and Dialectical Behavior Therapy (DBT), which add components of mindfulness and acceptance, draw on Stoic exercises that Ellis and Beck had originally underemphasised. The Serenity Prayer, written by Reinhold Niebuhr in 1932 — “grant me the serenity to accept the things I cannot change, the courage to change the things I can, and the wisdom to know the difference” — is the dichotomy of control rendered in twentieth-century devotional language.

What the evidence base now shows

The descendant of Epictetus’s teaching is now, by a substantial margin, the most empirically supported form of psychotherapy in modern medicine. Cognitive Behavioural Therapy has been tested in literally thousands of randomised controlled trials across the past five decades, covering depression, generalised anxiety disorder, panic disorder, post-traumatic stress disorder, obsessive-compulsive disorder, eating disorders, insomnia, chronic pain, and a long list of other conditions. The aggregate effect sizes from meta-analyses are typically in the moderate to large range, with Cohen’s d values between approximately 0.5 and 1.0 depending on the condition and the specific protocol. CBT is the first-line recommended treatment for several major mental-health conditions in clinical guidelines issued by the National Institute for Health and Care Excellence in the UK, the American Psychiatric Association, the American Psychological Association, and equivalent bodies across most developed countries.

As documented in the Robertson and Codd 2019 paper in The Behavior Therapist, the central therapeutic insight that runs through this entire empirical edifice — that emotional disturbance is mediated by judgements about events rather than by the events themselves, and that the path to reduced disturbance runs through revising the judgements rather than changing the events — is, in essentially its original form, what Epictetus was teaching his students in Nicopolis in the late first and early second centuries CE. The mechanism is the same. The vocabulary has changed. The clinical context has changed. The empirical infrastructure has changed beyond anything anyone in ancient Rome could have imagined. But the basic move at the heart of the intervention — sorting the things that are up to us from the things that are not, and reallocating attention accordingly — is recognisably the same move that opens chapter 1 of the Enchiridion.

What the framework asks

The practical implication for an ordinary person not currently in therapy is not that they should adopt the entire apparatus of clinical CBT. It is that the basic distinction Epictetus drew is available to anyone, costs nothing, and has been validated by approximately seventy years of clinical research and approximately two thousand years of philosophical practice. The exercise itself is straightforward. Whatever is currently troubling you — the conversation, the decision, the rejection, the diagnosis, the news, the relative, the political situation, the future you cannot guarantee — has two components. Some part of it is genuinely within your power to change. Some part of it is not. Sorting the two takes a few minutes of honest attention. Most of the suffering, in Epictetus’s account, comes from skipping that step. Most of the relief, in the modern CBT literature, comes from doing it.

The post The Stoic philosopher Epictetus taught that almost all human suffering comes from confusing the things we can control with the things we cannot — and the simple practice he proposed, of separating those two categories every morning before anything else, has quietly become the foundation of modern cognitive behavioral therapy nearly two thousand years later appeared first on Space Daily.

  •  

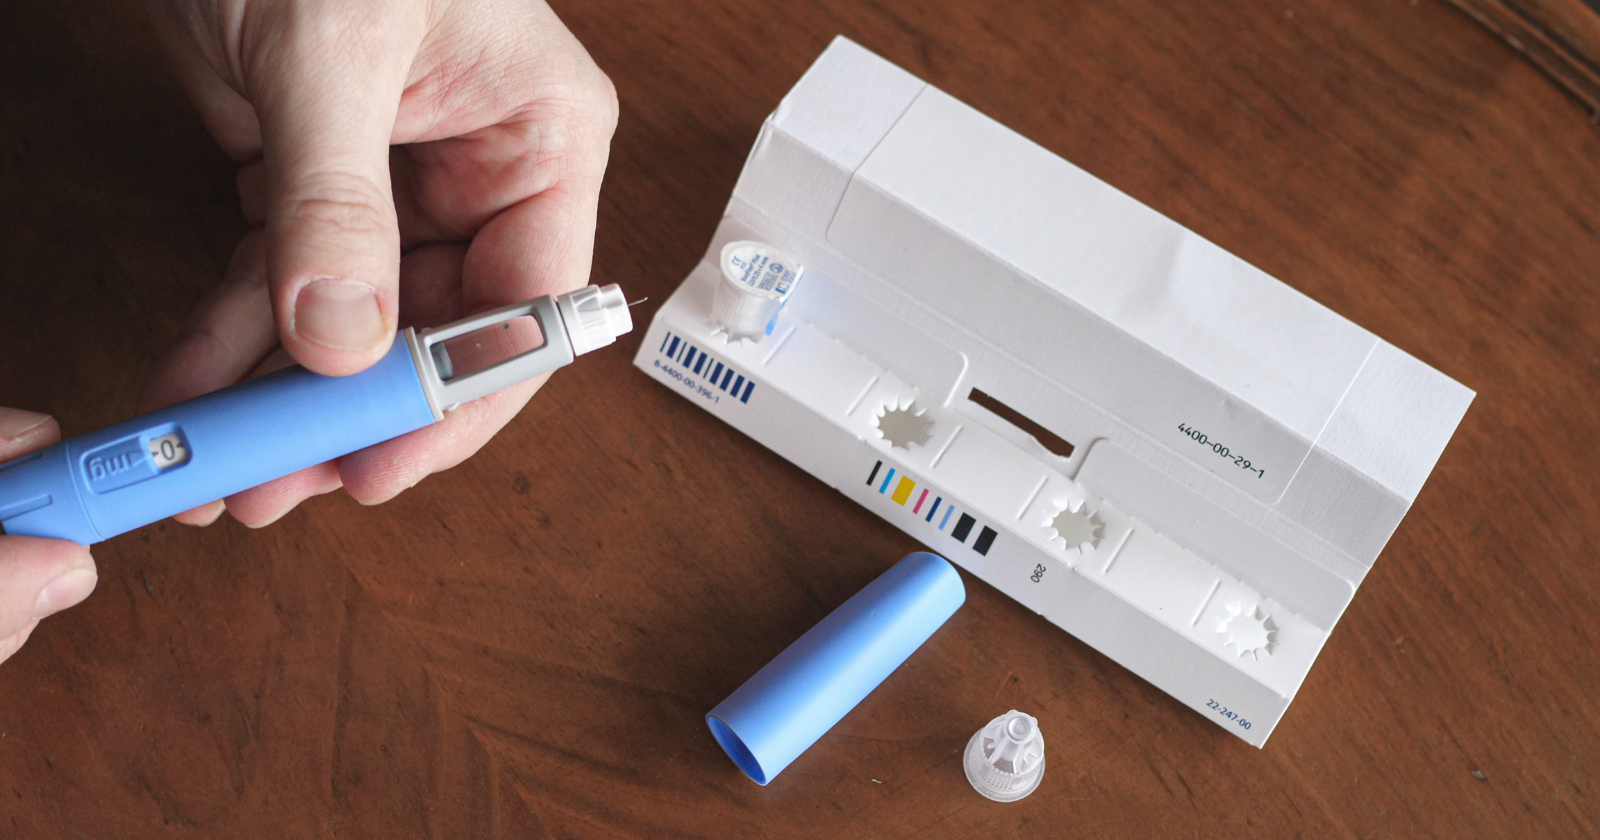
Ozempic was found in a 2025 clinical trial to reduce measurable biological age in adults by approximately 3 to 5 years — with improvements in inflammation, cardiovascular health, and kidney function — meaning a drug originally designed to manage blood sugar may turn out to be one of the first medications to formally extend human healthspan

The drug currently sweeping through the world’s prescription markets as a treatment for diabetes and obesity may turn out to do something its manufacturer never quite designed it for. In July 2025, a research team led by Michael J. Corley of UC San Diego, with Varun Dwaraka of the epigenetic-testing company TruDiagnostic as a key collaborator, published a preprint paper on medRxiv reporting the results of a randomized, double-blind, placebo-controlled clinical trial in which 108 adults received either weekly semaglutide injections — the active ingredient in Ozempic and Wegovy — or placebo, for 32 weeks. The work was subsequently published in Nature Communications in 2026. At the end of the trial, the participants who had received semaglutide showed measurable reductions in biological age across multiple validated epigenetic clocks, with an average reduction of approximately 3.1 years on the most-cited indices and up to 5 years on the most sensitive clocks. The placebo group showed no comparable changes. The trial is, by the researchers’ own characterization, the first direct clinical-trial evidence that a GLP-1 receptor agonist can modulate validated biomarkers of human aging.

According to the University of California’s press release on the study, the trial population was specifically people with HIV-associated lipohypertrophy — a condition in which excess fat builds up around the abdomen, and which is known to be accompanied by accelerated biological aging, persistent low-grade inflammation, and elevated cardiovascular risk. The choice of this population was deliberate. People with HIV-associated lipohypertrophy exhibit biological aging patterns substantially in excess of their chronological age, which makes them an unusually sensitive population for detecting any age-slowing effects of a candidate intervention. The 108 participants were randomized to either weekly semaglutide injections or matching placebo, with blood samples collected at baseline and at 32 weeks to enable detailed epigenetic age measurements before and after the intervention.

What the epigenetic clocks measured

The biological-age measurements in the trial were not based on subjective health indicators or simple physical metrics. They were based on DNA methylation patterns in the participants’ blood cells — chemical modifications that accumulate on the DNA over time and that have been validated across multiple independent studies as reliable indicators of biological age, mortality risk, and the rate at which a person’s body is aging. The trial used several different epigenetic clocks in parallel, each capturing slightly different aspects of the aging process. The first-generation clocks (Horvath clock and similar) measure cumulative biological age. The second-generation clocks (PhenoAge, GrimAge, PCGrimAge) are tuned to predict morbidity and mortality outcomes. The third-generation DunedinPACE clock measures the current rate at which aging is occurring, rather than the cumulative damage to date.

Per the original Corley et al. preprint on medRxiv, semaglutide produced the most pronounced effects on second-generation clocks predictive of morbidity and mortality risk, and on the third-generation DunedinPACE measure of biological aging rate, which slowed by approximately 9 percent in the treatment group. The first-generation clocks showed smaller but still measurable effects. The convergence of effects across multiple independent epigenetic measures is what gives the trial result its weight — semaglutide was not modulating a single biomarker that might have been a statistical artifact; it was modulating several at once, including the ones with the strongest established links to disease and mortality outcomes.

What the mechanism might be

The pathways by which semaglutide produces these aging-slowing effects are not yet fully characterized, but several converging hypotheses are now under investigation. The Corley team’s preprint identifies three plausible mechanisms. The first is reduced systemic inflammation — semaglutide treatment is associated with substantial reductions in inflammatory cytokines, and chronic low-grade inflammation is one of the central drivers of accelerated biological aging in the broader geroscience literature. The second is reduced visceral adipose tissue — the deep abdominal fat that secretes inflammatory and metabolically active molecules, and that has been independently linked to accelerated aging trajectories. The third is the modulation of what the authors call “obesogenic epigenetic memory” — the persistent epigenetic marks that obesity leaves on cells even after weight loss has occurred, and that may continue to drive accelerated aging long after the metabolic indicators have normalized.

As reported in Singularity Hub’s coverage of the trial, the magnitude of the semaglutide effect is comparable to the effects observed in the CALERIE trial of caloric restriction — the gold-standard randomized human trial of slowing biological aging through dietary intervention. The CALERIE participants, on approximately 12 percent caloric restriction for two years, showed approximately 2 to 3 percent slowing of biological aging on the DunedinPACE clock. The Corley semaglutide participants, on 32 weeks of weekly injections, showed approximately 9 percent slowing on the same clock. The convergence with the dietary-intervention literature suggests that semaglutide may be operating through some of the same metabolic pathways that caloric restriction does — reduced inflammation, reduced visceral fat, improved insulin sensitivity, modulation of mitochondrial function — but through pharmacological rather than dietary means.

What the trial does not establish

Honest framing requires several caveats. The study population was specifically people with HIV-associated lipohypertrophy, who exhibit elevated baseline biological aging — meaning the magnitude of the effect in a general adult population without accelerated-aging conditions is not yet established and could be smaller. The biological-age measurements are based on epigenetic biomarkers, which are well-validated as predictors of aging-related outcomes but are not themselves clinical outcomes. A 3-year reduction in epigenetic age is meaningful in terms of what it predicts about future mortality and disease risk, but it is not the same as a 3-year extension of measured lifespan, which would require multi-decade follow-up to confirm.

The trial also cannot fully disentangle the question of whether semaglutide is slowing aging directly, slowing aging indirectly through its effects on weight and metabolism, or both. As reported in Pharmaceutical Executive’s coverage of the trial, the participants who showed the largest reductions in biological age also tended to show the largest improvements in visceral fat, inflammatory markers, and metabolic indicators — suggesting that the age-slowing effect may be mediated by the metabolic improvements rather than being independent of them. Whether this distinction matters clinically depends on what one cares about: if the goal is slowing biological aging through any available means, the mechanism is less important than the outcome. If the goal is identifying a “pure” geroscience intervention that targets aging directly rather than indirectly, semaglutide may turn out to be more accurately described as an exceptionally effective metabolic drug whose age-slowing effects are downstream of its primary action.

Where this fits in the broader picture

The Corley trial is one of several recent findings positioning GLP-1 receptor agonists as candidate longevity drugs. The SELECT trial, published in 2024, followed 17,604 overweight people with cardiovascular disease for several years and found that semaglutide reduced major cardiovascular events by approximately 20 percent — an effect substantially larger than would be predicted by weight loss alone. A pilot study published in npj Aging in 2025 found that 42 percent of HIV-positive participants with metabolic dysfunction-associated steatotic liver disease showed reduced DunedinPACE aging rates on semaglutide. Additional trials in non-HIV populations, including the recently launched study at Zhejiang University comparing semaglutide and tirzepatide in obese adults without other conditions, are now underway to address the generalisability question that the 2025 Corley trial cannot answer on its own.

The next several years of GLP-1 research will determine whether semaglutide and similar drugs become routinely prescribed not just for diabetes and obesity but for the underlying biology of aging itself. If the early findings hold up across broader populations, the implications would be substantial: a class of drugs already approved by the FDA, already covered by major health insurers, already taken by an estimated 6 to 12 percent of US adults at last count, may turn out to be among the first medications in human history to formally extend healthspan in addition to treating the specific conditions for which they were originally designed. The 2025 Corley study is one piece of evidence in a longer chain of investigation, and the broader case is still being built. The biological signal, however, is now strong enough that the question is no longer whether to investigate semaglutide as a longevity drug, but how quickly the necessary trials can be designed, funded, and completed.

The post Ozempic was found in a 2025 clinical trial to reduce measurable biological age in adults by approximately 3 to 5 years — with improvements in inflammation, cardiovascular health, and kidney function — meaning a drug originally designed to manage blood sugar may turn out to be one of the first medications to formally extend human healthspan appeared first on Space Daily.

  •  

The neuroscience of intense romantic obsession shows that the brain in early-stage romantic love activates the same dopamine reward circuits as cocaine and gambling, with serotonin transporter levels indistinguishable from those of patients with obsessive-compulsive disorder, in a finding that explains why the experience feels involuntary and typically resolves within approximately 18 months regardless of outcome

The popular framing of intense romantic obsession treats it as an emotion, something that happens within the heart, that should be cultivated when reciprocated and resisted when unwelcome. The framing is intuitive and is the foundation of almost all of Western literature on romantic love. It is also, on the strongest reading of approximately twenty-five years of peer-reviewed neuroscience, inaccurate.

The state of intense romantic obsession is not, on the available evidence, an emotion. It is closer to what neuroscientists call a drive state, a category of brain activity that includes hunger, thirst, and the desire for sleep. Drive states are not voluntary. They are not reasoned. They are not regulated by the cognitive systems that humans use to evaluate evidence and make considered decisions. They are biological imperatives that operate on subcortical brain circuits and produce behaviour that the person experiencing them often describes as happening to them rather than being chosen by them.

The brain activity of someone in the early stages of intense romantic obsession is, on the available imaging evidence, biochemically and neurally closer to addiction than to love.

The Fisher fMRI study

The foundational peer-reviewed study of the neuroscience of romantic obsession was published in 2005 by the anthropologist Helen Fisher and her colleagues Arthur Aron and Lucy Brown in the Journal of Comparative Neurology, with the methodological details set out in a companion paper by the same team in the Journal of Neurophysiology in 2005. The team recruited 17 participants aged 18 to 26 who described themselves as intensely in love, with the duration of their romantic state ranging from one to seventeen months. Each participant was placed in a functional magnetic resonance imaging scanner and shown alternating photographs of the person they loved and photographs of a familiar but emotionally neutral acquaintance. The brain activity in response to each set of photographs was recorded and compared.

The activation specific to the beloved was concentrated in two brain regions. The first was the right ventral tegmental area, a small structure in the midbrain that produces and releases dopamine. The second was the right caudate nucleus, a subcortical structure involved in reward processing, goal pursuit, and the formation of habits. Both regions are part of the brain’s mesolimbic dopamine reward system, the same neural network that is activated by cocaine, by gambling wins, by sugar consumption, and by the anticipation of receiving any other strong reward.

The Fisher team noted that the activation pattern in romantic love was not identical to addiction but was substantially overlapping. The brain regions involved were the same. The neurotransmitter system involved was the same. The behavioural patterns produced, including obsessive thinking about the source of the reward, craving for contact, emotional dependence on signs of reciprocation, and difficulty regulating attention to anything else, were the same. What was different was the source of the reward. The brain did not appear to distinguish, at the level of reward-system activation, between the chemical reward of cocaine and the social reward of a particular person.

The Fisher team also noted, in subsequent analyses of the same data, that the prefrontal cortex regions involved in critical judgment and skeptical evaluation showed reduced activation during exposure to images of the beloved. The brain was activating the reward system at full intensity while simultaneously quieting the evaluative system that would otherwise check the reward-driven impulses.

The Marazziti serotonin finding

The Fisher fMRI findings on dopamine were preceded by a different and equally striking peer-reviewed finding from a research team at the University of Pisa in Italy. In 1999, Donatella Marazziti and colleagues published a study in Psychological Medicine that examined a different neurotransmitter system. The team recruited 20 participants who had fallen in love within the previous six months, 20 patients with severe obsessive-compulsive disorder, and 20 controls matched for age and sex. The team measured the platelet serotonin transporter density in each group, which is one of the most reliable available indicators of central serotonin system function.

The serotonin transporter levels in the people who had recently fallen in love were approximately 40 per cent lower than in the controls. The serotonin transporter levels in the patients with severe obsessive-compulsive disorder were also approximately 40 per cent lower than in the controls. The two groups, on the laboratory measurements used, were biochemically indistinguishable from each other.

The Marazziti finding, which won the Ig Nobel Prize for Chemistry in 2000 and has since been broadly confirmed in subsequent peer-reviewed work, established that the obsessive-thinking patterns of intense romantic love are not metaphorically similar to obsessive-compulsive disorder. They are biochemically indistinguishable from it at the level of the serotonin transporter system. The popular language of “love sickness” and “love-crazed” turns out to have been more accurate, in the literal neurochemical sense, than the popular sentimental language of love.

The Marazziti team also followed their subjects over time and found that the lowered serotonin transporter levels returned to baseline within approximately 12 to 18 months from the initial measurement, regardless of whether the romantic relationship continued. The biochemical state that produced the obsessive thinking was time-limited.

The 18-month rule

The finding that intense romantic obsession is biologically self-limiting has been one of the most consistently replicated results in the neuroscience of love. The dopaminergic activation in the ventral tegmental area and caudate nucleus, on the longitudinal data, does not maintain its intensity indefinitely. It typically remains elevated for approximately 12 to 24 months and then declines toward baseline. The serotonin transporter suppression follows a similar curve. The cortisol elevation, which is the third major neurochemical signature of early-stage romantic love, also resolves within approximately the same period.

The 18-month rule, as it is sometimes called in the popular psychology literature, was first proposed by Dorothy Tennov in her 1979 book Love and Limerence: The Experience of Being in Love. Tennov, based on more than a decade of interviews with approximately 500 subjects, observed that the most intense phase of romantic obsession, which she called limerence, typically resolved within 18 months to 3 years regardless of whether the relationship continued. Her observation was based on qualitative interview data and was not, at the time of publication, supported by neurochemical evidence.

The peer-reviewed neuroscience of the past twenty-five years has substantially confirmed Tennov’s observation. The dopaminergic, serotonergic, and cortisol changes that produce intense romantic obsession are not sustained by ongoing relationship presence or by ongoing relationship absence. They are sustained by the brain’s own time course, which is approximately one to three years. The relationship may continue past that point, in which case the intense obsessive state transitions into a different and more sustainable neurochemical pattern centred on oxytocin, vasopressin, and the attachment system. The relationship may end before that point, in which case the intense obsessive state continues for the remainder of its biological course and then resolves on its own.

The implication is that the experience the popular psychology literature has called limerence is not, primarily, a fact about the other person. It is a fact about the limerent person’s brain, which has entered a specific neurochemical state that will persist for a specific period of time before returning to baseline.

A short video we came across goes into the psychology behind limerence, breaking down exactly what it is and how its effects can be so powerful – click here to watch it. 

What this means for the involuntary feeling

The peer-reviewed neuroscience also explains a feature of intense romantic obsession that has been described consistently across cultures and centuries: that it does not feel chosen. The classical and Renaissance literature on love is full of metaphors of being struck by arrows, possessed by spirits, or driven mad by external forces. The popular contemporary language uses similar metaphors of falling, being captured, being unable to help oneself.

The metaphors are, on the available evidence, broadly accurate descriptions of what is happening at the neural level. The reward system is being activated involuntarily, by stimuli the person has not chosen and cannot turn off. The evaluative system that would normally regulate the impulses produced by reward activation is partially deactivated. The neurochemical state is being sustained by the brain’s own time course rather than by any decision the person is making.

The state of intense romantic obsession, in other words, is happening to the person rather than being performed by them. The person can choose what to do with it. They cannot choose to have it or not have it, and they cannot, on the available evidence, choose how long it lasts.

The honest limitations

Several caveats apply to the literature described above.

The Fisher 2005 fMRI study had a sample size of 17 participants, which is small by contemporary neuroscience standards. The findings have been broadly replicated in subsequent work, including the Fisher, Brown, Aron, Strong, and Mashek 2010 follow-up study in the Journal of Neurophysiology that examined the brains of people who had recently been rejected in love, but no individual study in this field has the kind of large sample size that would constitute definitive evidence. The conclusions are supported by a body of converging evidence rather than by any single decisive experiment.

The Marazziti 1999 finding on serotonin transporters was based on a platelet measurement, which is an indirect indicator of central serotonin function rather than a direct measurement of brain serotonin activity. The interpretation that the platelet finding reflects brain serotonin activity is plausible and is the standard interpretation in the literature, but it is not definitively established.

The concept of limerence, as developed by Dorothy Tennov, is not a recognised clinical diagnostic category in the current Diagnostic and Statistical Manual or the International Classification of Diseases. The phenomena Tennov described are real and have been substantially confirmed by subsequent neuroscience, but mainstream clinical psychology has largely absorbed them into adjacent frameworks including early-stage romantic love, obsessive-compulsive spectrum disorders, and anxious attachment patterns, rather than maintaining limerence as a distinct category.

The 18-month rule is a statistical central tendency rather than a deterministic timeline. Some individuals experience the intense obsessive phase for substantially shorter periods, and some experience it for substantially longer. The biological mechanisms involved are self-limiting in general but operate on different schedules in different people.

What it means

Several things follow from the neuroscience of intense romantic obsession that are worth saying clearly.

The first is that the experience that the popular psychology literature has called limerence is a real biological phenomenon with measurable neurochemical correlates. It is not a moral failure, a sign of weakness, or a psychological aberration. It is a specific state of the human brain that has been documented across cultures, across history, and across the available neuroscience evidence.

The second is that the involuntary quality of the experience is also real. The dopaminergic reward system is being activated subcortically, by mechanisms that operate beneath conscious decision-making. The serotonergic obsessive-thinking system is being suppressed by mechanisms that operate beneath conscious decision-making. The cortisol stress response is being elevated by mechanisms that operate beneath conscious decision-making. None of these systems can be turned off by willpower.

The third is that the experience is also, by the available evidence, time-limited. The neurochemical state that produces intense romantic obsession is biologically self-limiting in ways that are unique to the early stages of romantic love. It will end. The available timeline is approximately 12 to 18 months for most people, with substantial individual variation. What the person does during that period is partly under their control. What they feel during that period is largely not.

The fourth, on the strongest current reading of approximately twenty-five years of peer-reviewed evidence, is that the relationship between the popular sentimental language of romantic love and the underlying neuroscience is more honest than the relationship between the popular sentimental language and the underlying experience.

The brain in intense romantic obsession is, by the available evidence, doing what the classical literature has always said love does to people.

It is just doing it through dopamine, serotonin, and cortisol rather than through arrows.

The post The neuroscience of intense romantic obsession shows that the brain in early-stage romantic love activates the same dopamine reward circuits as cocaine and gambling, with serotonin transporter levels indistinguishable from those of patients with obsessive-compulsive disorder, in a finding that explains why the experience feels involuntary and typically resolves within approximately 18 months regardless of outcome appeared first on Space Daily.

  •  

Researchers identified a personality profile that combines high empathy with high levels of narcissism, Machiavellianism, and psychopathy, in a finding that has complicated the standard scientific picture of empathy as an unambiguously prosocial human trait

The popular assumption about empathy, repeated across most of contemporary psychology, ethics, education, and public discourse, is that it is one of the unambiguously good human capacities. The empathic person feels what other people feel, understands their suffering, and is for that reason motivated to act in ways that reduce suffering rather than cause it. The assumption is intuitively appealing and, until recently, has been broadly shared across most of the scientific and clinical disciplines that study human behaviour.

The peer-reviewed evidence of the past two decades has substantially complicated the picture.

Empathy, on the strongest current reading of the social neuroscience and personality literature, is selective rather than universal. It is exhaustible rather than inexhaustible. It is exploitable rather than reliable. And in some cases, it can be one of the cognitive resources that the most dangerous personalities in the population use most effectively against the people they are harming.

The Heym 2020 study

In 2020, Nadja Heym and colleagues at Nottingham Trent University published a peer-reviewed study in the journal Personality and Individual Differences that used a statistical technique called latent profile analysis to identify distinct personality patterns within a sample of 991 adults. The participants completed standardised measures of empathy and of the three personality traits collectively known as the Dark Triad: narcissism, Machiavellianism, and psychopathy. The Dark Triad has been studied since the early 2000s as a cluster of socially aversive but non-clinical personality traits that show consistent associations with manipulation, exploitation, and reduced concern for others.

The standard assumption in the personality literature, before the Heym study, was that high empathy and high Dark Triad traits were essentially mutually exclusive. The empathic person was, by definition, not the narcissistic or Machiavellian person. The latent profile analysis tested this assumption.

It did not hold up.

The Heym team identified four distinct profiles in the sample. The Typicals (approximately 34 per cent) had moderate empathy and low Dark Triad traits. The Empaths (approximately 33 per cent) had high empathy and low Dark Triad traits. The Dark Triad group (approximately 13 per cent) had low empathy and high Dark Triad traits, matching the standard assumption in the literature. The fourth group, comprising approximately 19 per cent of the sample, had high empathy combined with high Dark Triad traits. The team called this group the Dark Empaths.

The Dark Empaths were not a hypothesised construct or a clinical category. They were a statistical pattern that emerged from the data, in approximately one in five participants. The proportion has since been broadly replicated in follow-up studies on samples from different countries.

What the dark empath profile actually shows

The follow-up analyses in the Heym study found that Dark Empaths shared some characteristics with each of the other two relevant groups but differed from both in specific ways. Like the standard Dark Triad group, the Dark Empaths showed elevated rates of indirect aggression, including gossip, rumour spreading, social exclusion, and the strategic damage of other people’s reputations. Like the standard Empaths, they showed higher emotional understanding of others and more accurate perception of other people’s mental states.

The combination produced what the team described as an “antagonistic core with empathy.” The Dark Empaths were not simply Dark Triad individuals with a softer surface presentation. The empathy was real, on the measurement instruments used. What distinguished the Dark Empaths from typical empaths was not the absence of empathy but the use to which empathy was put.

Empathy, on this reading, is a cognitive tool. It can be used to identify suffering in others and to reduce that suffering. It can also be used to identify suffering in others and to exploit it. The Heym team’s evidence suggests that approximately a fifth of the adult population is using it for the second purpose at least as often as the first, even while scoring as highly empathic on standard measures.

A short video explains more about the psychology behind dark empaths and why they are so hard to spot – click here to watch it.

Empathy is selective

The Dark Empath finding sits within a broader scientific reassessment of empathy that has been gathering peer-reviewed evidence for approximately two decades.

The most fundamental challenge to the popular framing comes from the social neuroscience research showing that empathy is selective rather than universal. Functional magnetic resonance imaging studies have consistently found that the same neural circuits that activate when a person observes pain in an in-group member fail to activate, or activate substantially less, when the same person observes pain in an out-group member. The effect has been measured across racial, national, religious, political, and team-affiliation categories. People do not, on the neural evidence, feel the same empathy for everyone. They feel substantially more empathy for people who are like them.

The selective activation of empathy is one of the most consistently replicated findings in social neuroscience. It also has direct implications for how empathy operates as a moral guide. A moral system based on empathy is, by the neural evidence, a system that systematically over-weights the suffering of the in-group and under-weights the suffering of the out-group. This is not a bug in the empathy system. It appears to be how the empathy system was designed by evolution to operate.

Empathy is exhaustible

The second major challenge to the popular framing comes from the empathy fatigue research. Tania Singer and Olga Klimecki of the Max Planck Institute for Human Cognitive and Brain Sciences published a foundational paper in Current Biology in 2014 that examined the neural and behavioural consequences of sustained exposure to the suffering of others. The findings, which have since been replicated across multiple populations, indicate that prolonged empathic engagement with suffering activates the same neural pain pathways in the empathiser as in the person being empathised with. Over time, sustained empathic engagement produces measurable distress, anxiety, and depression in the empathiser.

The Singer and Klimecki paper made a further distinction that has become increasingly important in the empathy literature. Empathy, in the technical sense the team used, is the affective sharing of another person’s emotional state. Compassion is different. Compassion involves caring about the suffering of others without sharing it in the same direct affective sense. The two states activate different neural networks. Empathy activates the anterior insula and anterior cingulate cortex, the same regions that process physical pain. Compassion activates the ventral striatum, the medial orbitofrontal cortex, and the ventral tegmental area, the regions that process reward and motivated action.

The practical implication of the distinction is that compassion is sustainable in ways that empathy is not. The healthcare worker who maintains compassion for patients across a thirty-year career does not do so by feeling the patients’ pain on an ongoing basis. The patients’ pain, sustained at that intensity over decades, would damage the worker’s mental health. What the long-career healthcare worker has typically learned to do is to care for patients without sharing their distress, which is a different and more durable cognitive state.

The Bloom case

The most prominent recent popular articulation of these findings is the 2016 book Against Empathy: The Case for Rational Compassion by the Yale psychologist Paul Bloom. The book drew on the social neuroscience and personality research described above to argue that empathy, properly defined, is a poor guide to moral judgment. Bloom argued that the same evidence supporting empathy’s selectivity and exhaustibility also supported a substantial reorientation of how psychology and ethics should treat empathy.

The Bloom argument is not that empathy is bad. The argument is that empathy is a specific cognitive capacity that operates in specific ways and has specific consequences, some of which are good and some of which are not. The popular framing in which empathy is the moral foundation of human goodness does not survive contact with the empirical evidence. What does survive contact with the evidence is a more limited claim: empathy is one of several cognitive resources that humans use in their social and moral lives, with both benefits and costs that depend on how it is deployed.

The Bloom case has been contested by other researchers, including the developmental psychologist Jamil Zaki of Stanford University, who argues that empathy can be trained and refined rather than abandoned. The disagreement is genuine and ongoing in the peer-reviewed literature. What is not in dispute is that the previous consensus, in which empathy was treated as unambiguously good and the only question was how to increase it, is no longer scientifically defensible on the available evidence.

The honest limitations

Several methodological caveats apply to the literature described above.

The Dark Empath construct, while peer-reviewed, is relatively new. The Heym 2020 study has been replicated in some follow-up work but not yet across the breadth of populations and cultures that would establish it as a robust personality category. The 19 per cent proportion identified in the original sample may differ in samples from other cultures, age groups, or socioeconomic contexts. The construct is genuinely supported by the available evidence but should be treated as a current scientific hypothesis rather than as an established personality category.

The neural research on empathy and compassion, while strong, is based largely on laboratory measures of brief emotional responses to specific stimuli. The relationship between laboratory neural patterns and the empathy people actually exercise in their daily lives is plausible but not perfectly direct. The Singer and Klimecki framework has been broadly accepted in social neuroscience but is not the only available model.

The in-group and out-group selectivity of empathy has been measured robustly but is also context-dependent. The same individual can show strong empathy for an out-group member in some circumstances and reduced empathy for the same person in others. The selectivity is not a fixed personality trait but a context-sensitive cognitive bias.

What it means

Several things follow from the differentiated picture of empathy that are worth saying clearly.

The first is that empathy is not, on the strongest current reading of the evidence, a reliable moral compass. It is a cognitive capacity that operates selectively, depletes with use, and can be deployed by people whose intentions are not aligned with the welfare of those they are empathising with. The popular framing in which empathy is the foundation of human goodness underestimates each of these complications.

The second is that the alternative the peer-reviewed literature points to is not the abandonment of empathy but the recognition that compassion is a distinct and more durable mental state. Compassion does not require feeling another person’s pain. It requires caring about another person’s welfare. The distinction has measurable neural correlates and measurable practical consequences for how the two capacities can be sustained across time.

The third is that the existence of the Dark Empath profile, which approximately a fifth of adults appear to display, has practical implications for how individuals navigate their personal and professional relationships. The standard heuristic that emotional understanding equals safety is not, on the available evidence, reliable. Someone can read another person’s emotional state with substantial accuracy and use that reading to manipulate rather than to help. The popular framing that the most dangerous personalities are emotionally cold is, on the Heym evidence, incomplete. Some of them are emotionally warm and using that warmth strategically.

The fourth, on the strongest current reading of fifty years of research that has now substantially shifted in its conclusions, is that empathy is real, important, and useful, but it is not what it has been popularly assumed to be. It is one cognitive tool among several, with specific properties that determine how it operates and what it can and cannot do.

What it cannot do, by the available peer-reviewed evidence, is reliably tell us who is trustworthy and who is not.

The post Researchers identified a personality profile that combines high empathy with high levels of narcissism, Machiavellianism, and psychopathy, in a finding that has complicated the standard scientific picture of empathy as an unambiguously prosocial human trait appeared first on Space Daily.

  •  
❌